
Video demonstration
Inspection
- Assess the patient standing and walking. Assess the longitudinal arch of the foot and see if there is sufficient clearance from the calcaneus to the head of the 1st metatarsal (high arch or flatfoot). Assess the transverse arch by checking if the MTP joints of the 2nd and 3rd rays are more flattened than the 4th ray. Assess in-toeing or out-toeing. Normal out-toeing is 12-18°. In-toeing is most often caused by increased anteversion in the hip joint. Assess the angle between the Achilles tendon and the center of the calcaneus, normally 0-4° valgus. Increased valgus (calcaneovalgus) corresponds with a reduced longitudinal arch in the foot.
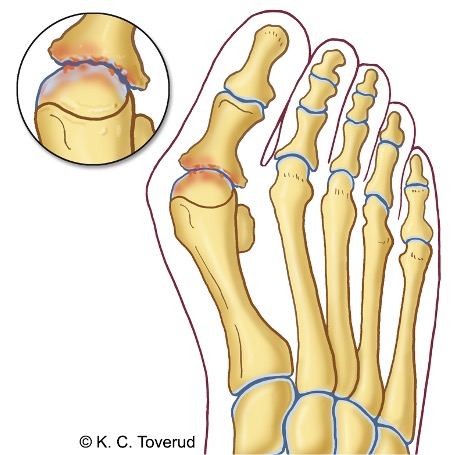
- Consider Gait pattern, malpositions, axis deviations, pain during load. Check the longitudinal arch and assess whether there is flatfoot (pes planus) or high arch (pes cavus). Check the transverse arch and assess whether there is transverse flatfoot (transversus planus). Determine whether there is in-toeing or out-toeing as a sign of rotational deviation in the hip joint. Normally, there is 12-18° out-toeing. Evaluate the Achilles tendon angle, which should normally be between 0-4° valgus. Determine whether there are clinical signs of hallux valgus with a valgus angle >15°.
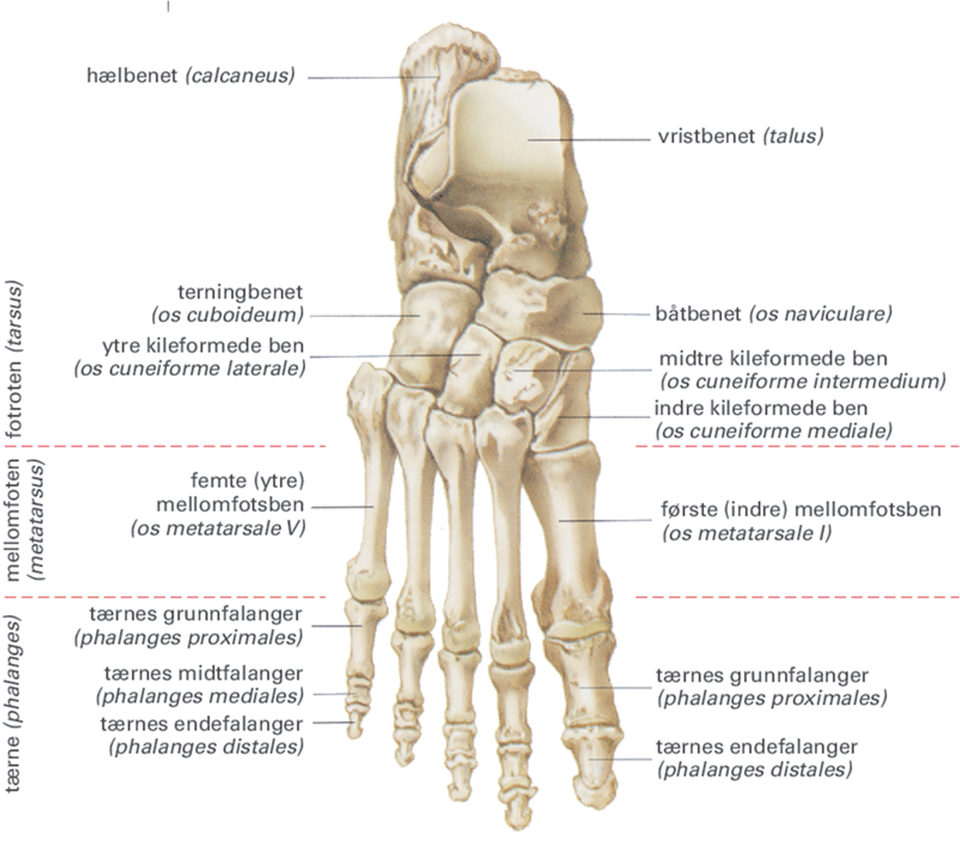
Ankle and foot anatomy, 26 bones, 33 joints
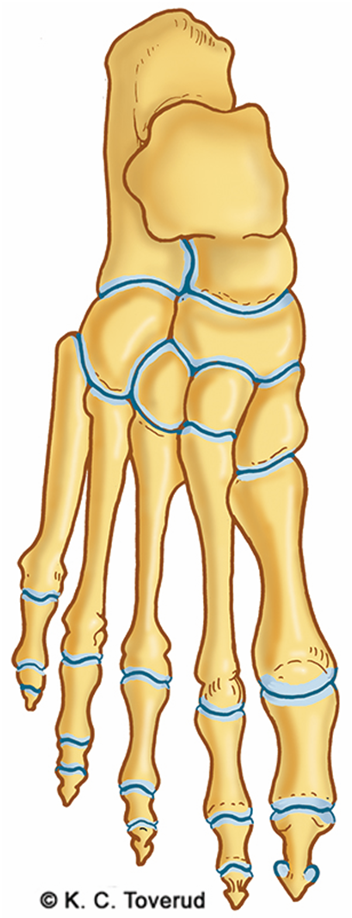
Ankle and foot anatomy
Hallux valgus
Medially
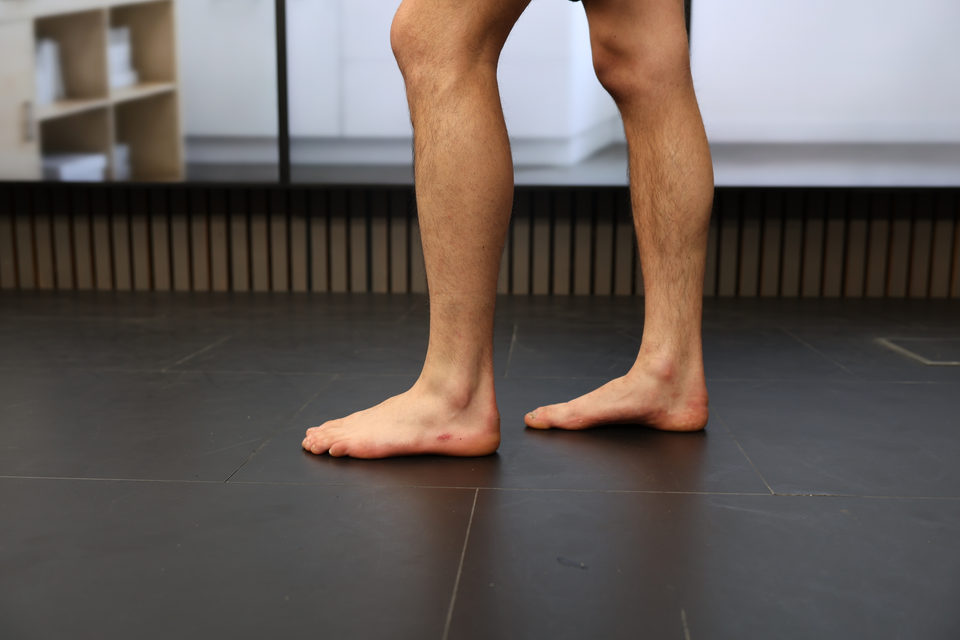
Assess the longitudinal arch of the foot and see if there is sufficient space from the calcaneus to the head of the 1st metatarsal. If there is little space along the medial arch of the foot, there is a flatfoot. If there is a large space along the medial arch of the foot, there may be a high arch.
From the front

Assess the transverse arch by checking if the metatarsophalangeal joints of the 2nd and 3rd toes are flatter than that of the 4th toe. If the transverse arch is collapsed, there is a transverse flatfoot.
Assess whether there is in-toeing or out-toeing. Normal is 12–18° out-toeing.
From the back

Evaluate the angle between the Achilles tendon and the center of the calcaneus; normally it is 0–4° valgus. Increased valgus (calcaneovalgus) often corresponds with a reduced longitudinal arch in the foot (flatfoot).
Active movements
- Assess To test movements while seated, ensure good support so that the movement is isolated to the ankle joint. Record range of motion and pain. This provides a first impression of whether the problem is in the ankle joint, the muscles, or is referred from the foot, calf, or knee.
- Consider Whether reduced range of motion in the ankle joint is due to muscular conditions (tight Achilles tendon or hamstring muscles), a consequence of ankle sprain (capsular tightness), ligament injury, or osteoarthritis.
Plantar flexion
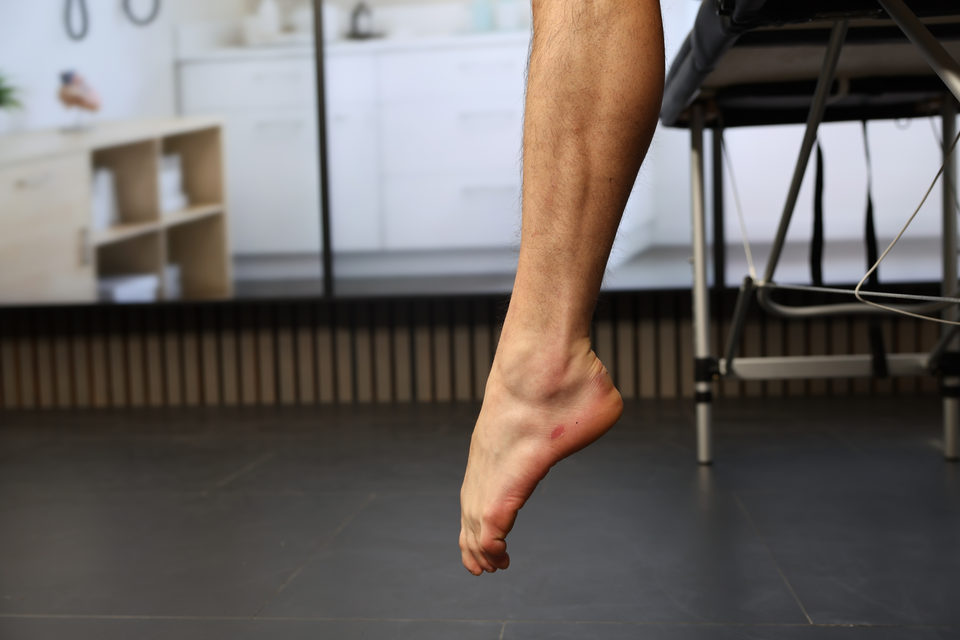
Ask the patient to plantarflex the ankle.
Dorsiflexion
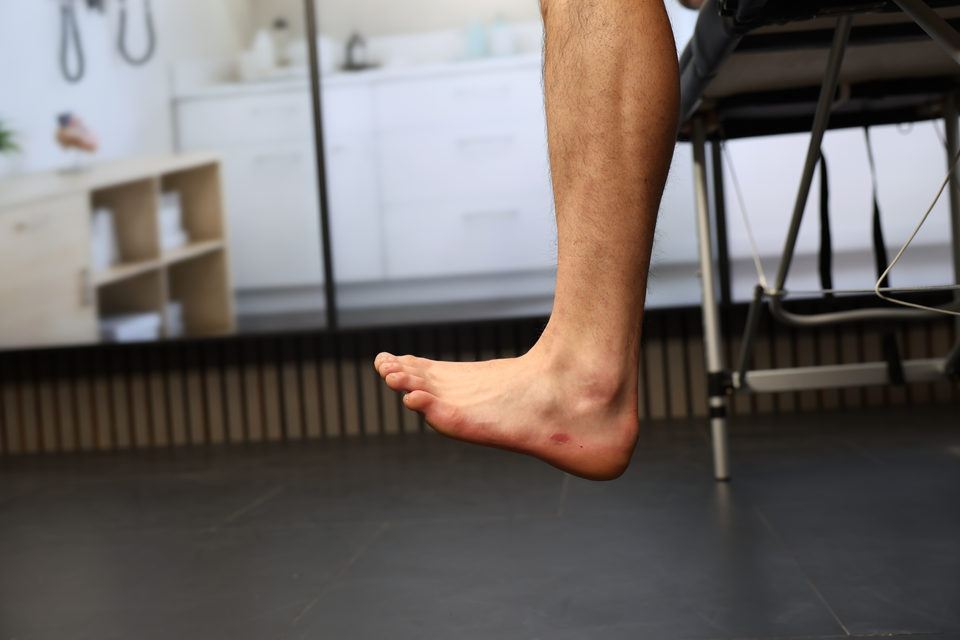
Ask the patient to dorsiflex the ankle.
Inversion
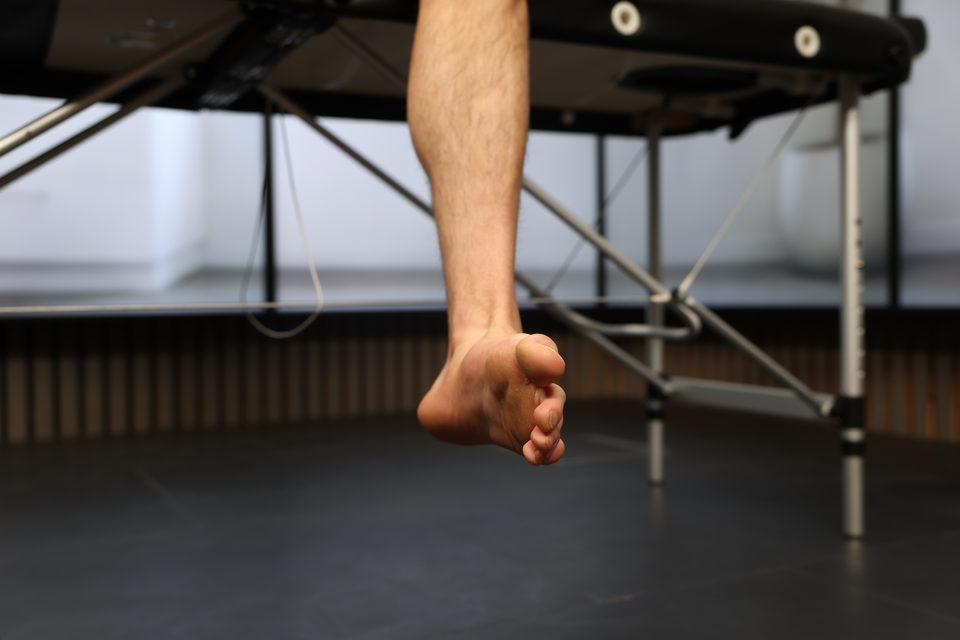
Ask the patient to invert the ankle/forefoot.
Eversion

Ask the patient to evert the ankle/forefoot.
Passive movements
- Assess to stabilize the tibia and fibula so that the movement is isolated to the ankle joint. Record range of motion, pain, end-feel, and asymmetry. Consider testing in supine position with the knee slightly flexed during dorsiflexion to reduce tightness in the gastrocnemius. Consider interpreting the findings in light of previous trauma, foot position (flatfoot/high arch), and symptoms during walking and load-bearing. Reduced dorsiflexion in the ankle is associated with increased risk of overuse injuries and altered movement patterns throughout the lower extremity.
- Consider the end-feel in the range of motion. Normal end-feel is soft and elastic. Determine whether passive movement triggers pain at the front of the ankle joint (capsular irritation), at the back (Achilles tendinopathy), laterally (anterior talofibular ligament), or medially (deltoid ligament, posterior tibialis). Determine if there is pain with dorsiflexion of the big toe (hallux rigidus, osteoarthritis, capsulitis). Dorsiflexion of the big toe is essential for the push-off phase in walking. Reduced movement can cause altered gait patterns, forefoot pain, and compensatory issues in the ankle and calf.
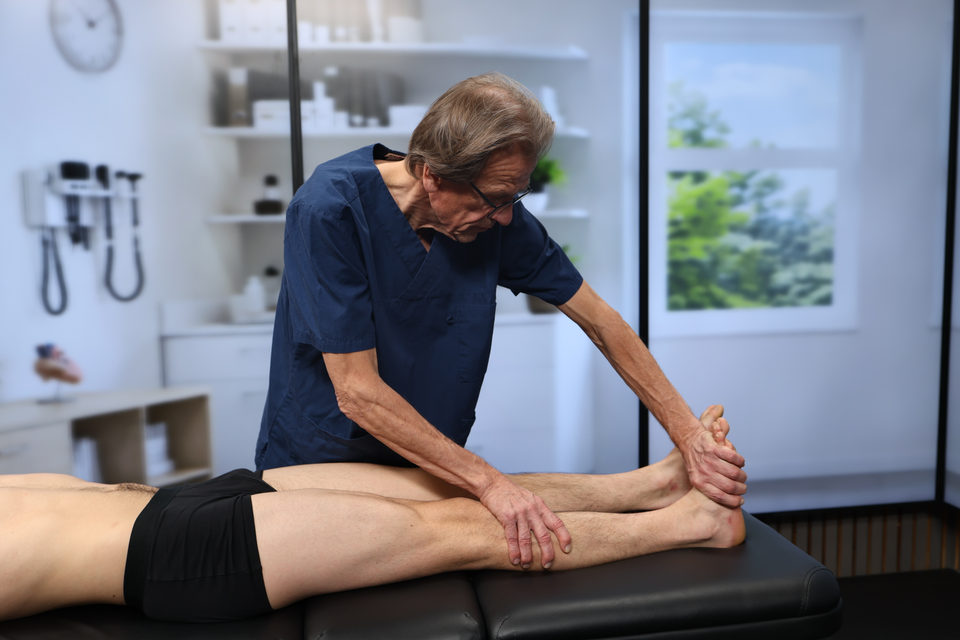
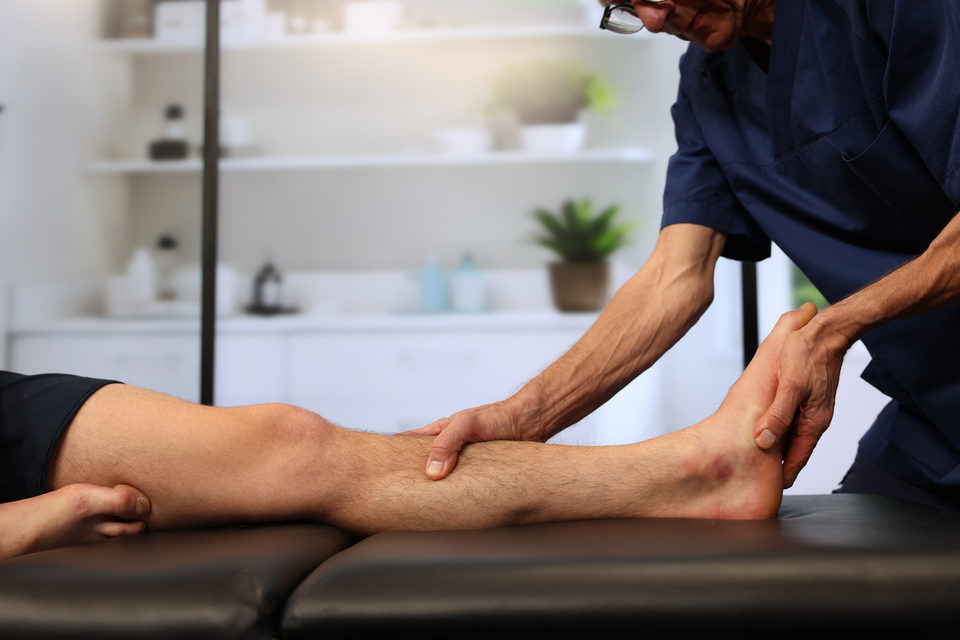
Dorsiflexion 5–40°
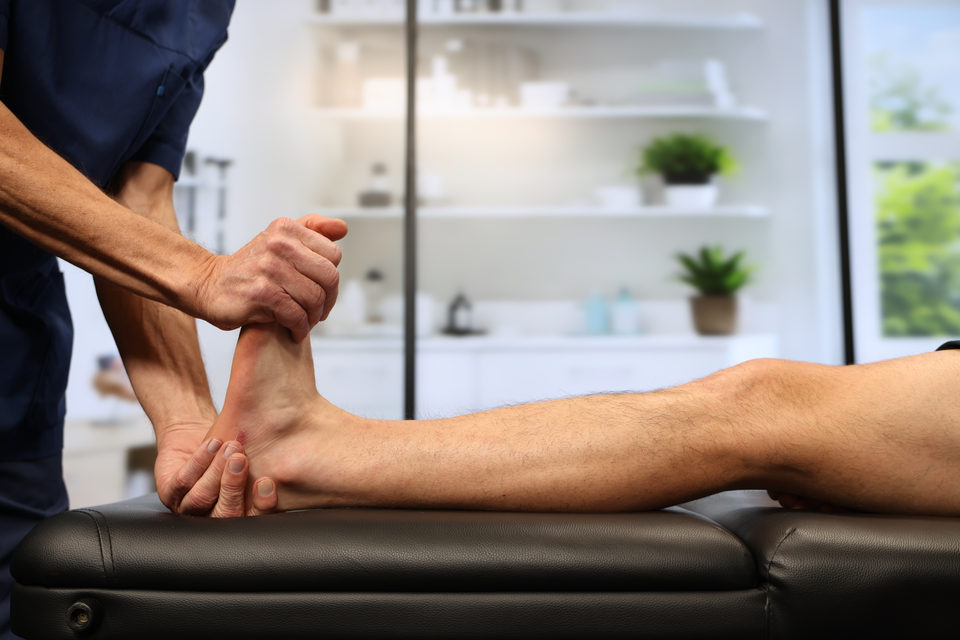
The patient is lying on their back with slight flexion in the knee joint. The examiner holds one hand posteriorly distal on the leg and moves the ankle joint into dorsiflexion with the other hand.
Plantar flexion 10–55°
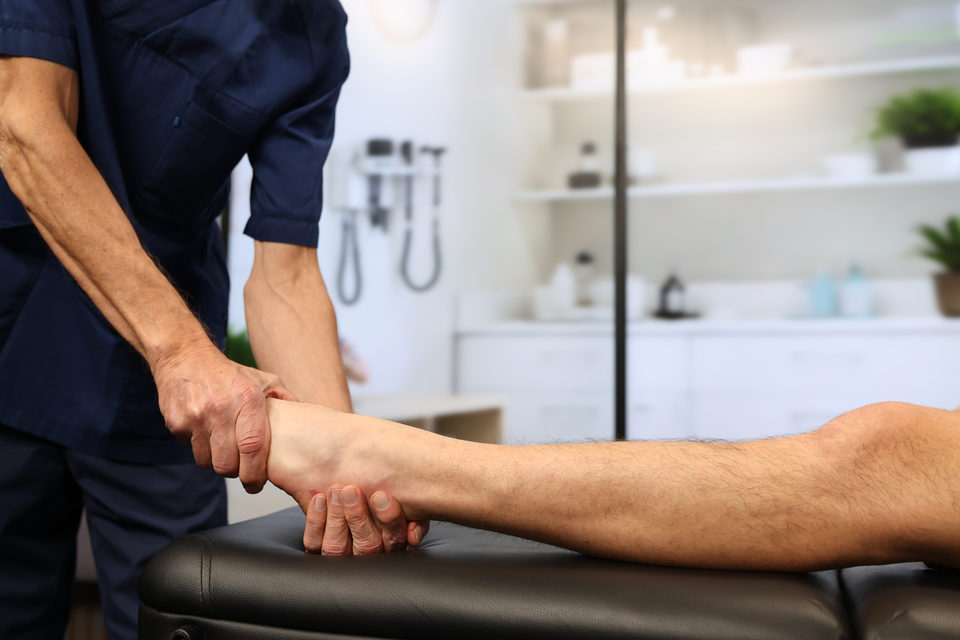
The patient is lying on their back. The examiner grasps the patient's heel with one hand and plantar flexes the ankle joint with the other hand.
Eversion 15–50°
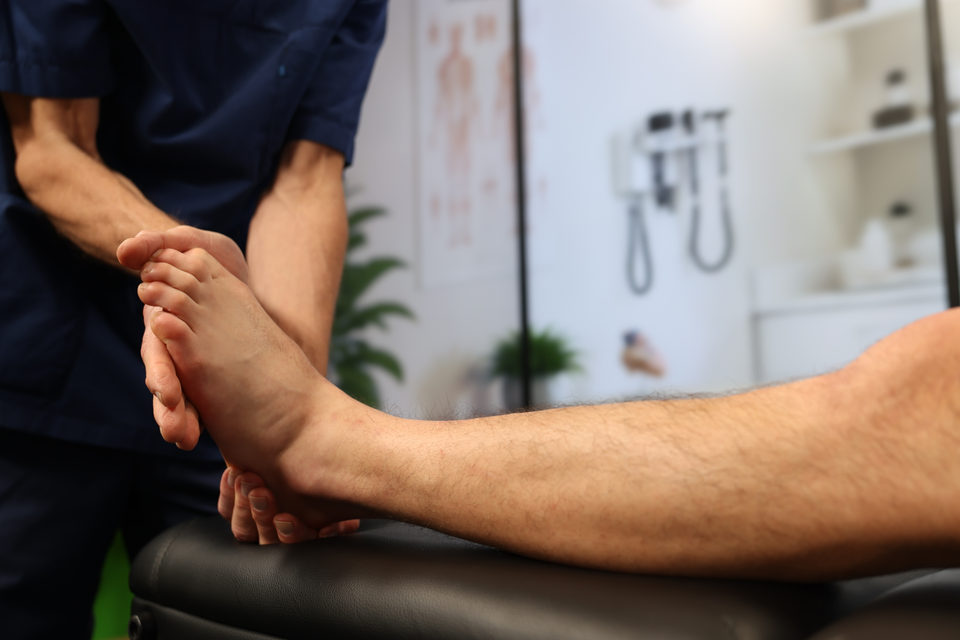
The patient is lying on their back. The examiner stabilizes the ankle joint laterally and moves the ankle and forefoot with the other hand into eversion.
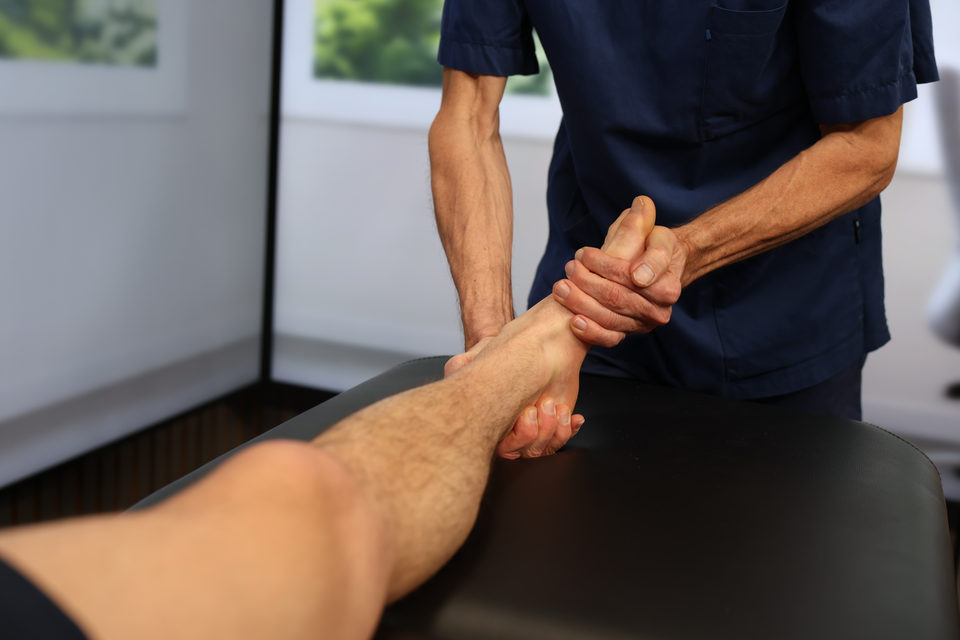
Inversion 15–50°
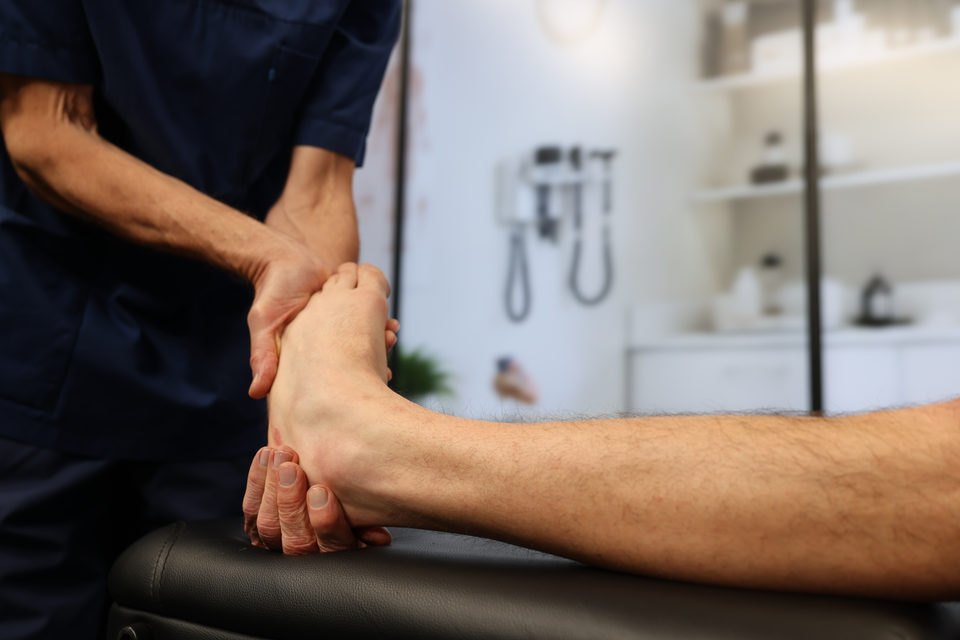
Patient on back. The examiner stabilizes the ankle joint medially and moves the ankle and forefoot into inversion with the other hand.
Passive range of motion ankle
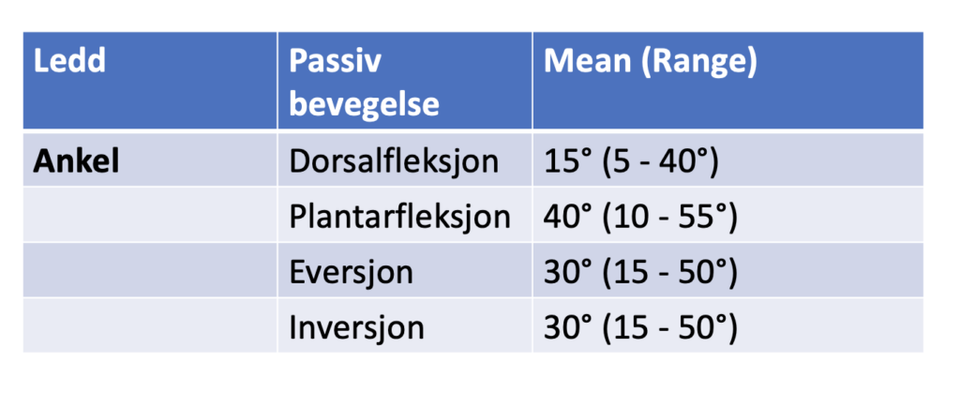
of the Hip, Knee and Ankle Joints in Male Subjects, 30–40 Years of Age, Acta Orthopaedica Scandinavica, 53:2, 205-208
Big toe flexion
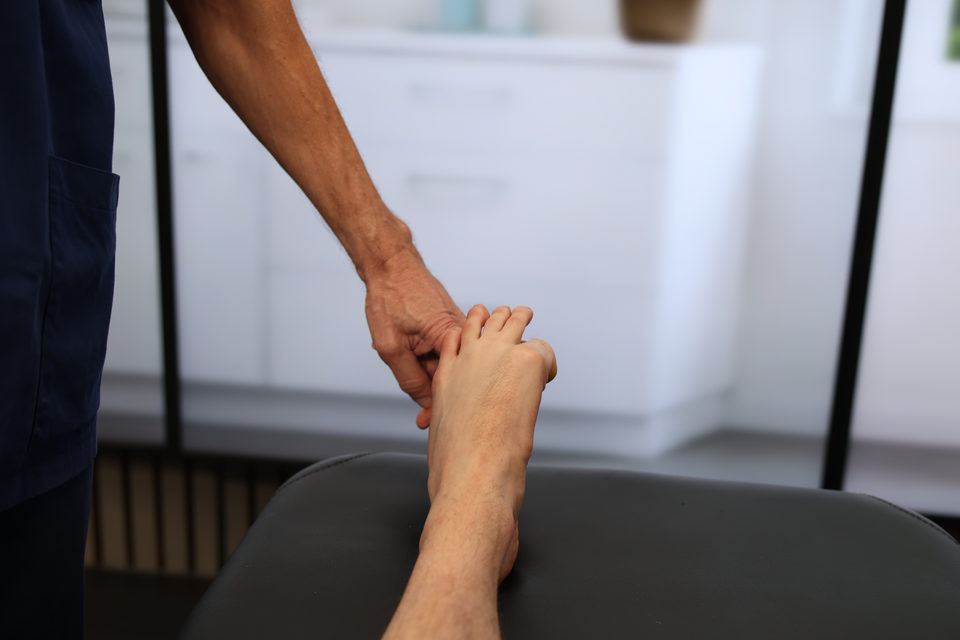
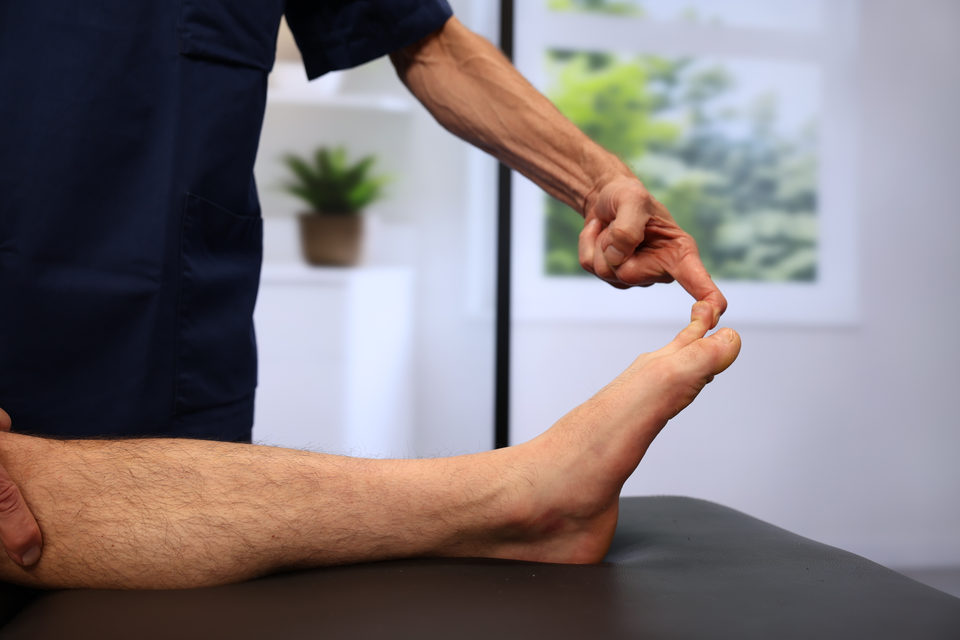
Patient on back. The examiner moves the big toe into plantar flexion.
Big toe extension
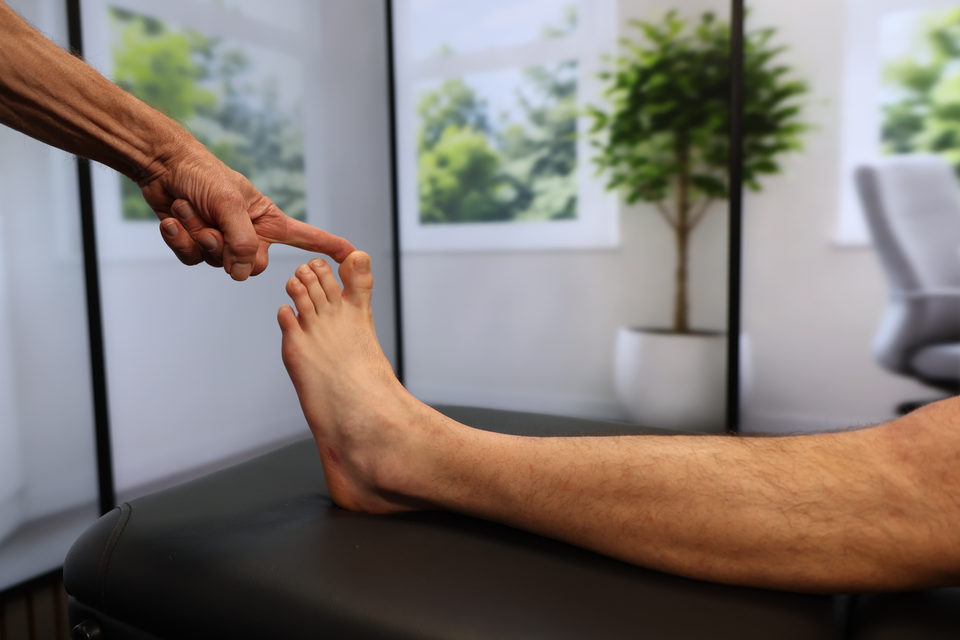
Patient on back. The examiner moves the big toe into dorsiflexion.
Toe flexion
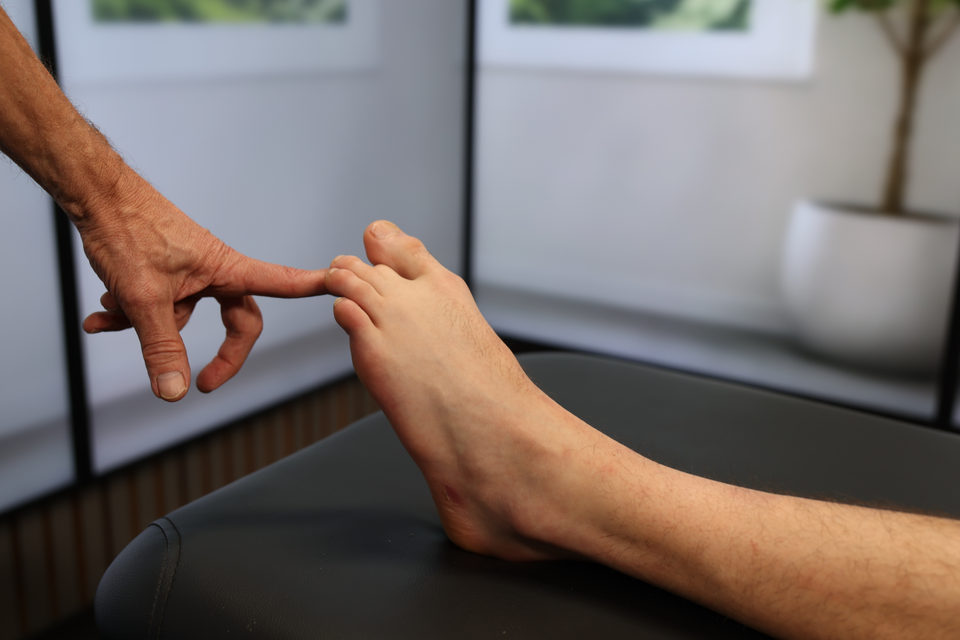
Patient on back. The examiner moves the second toe into flexion. Repeated for third to fifth toes.
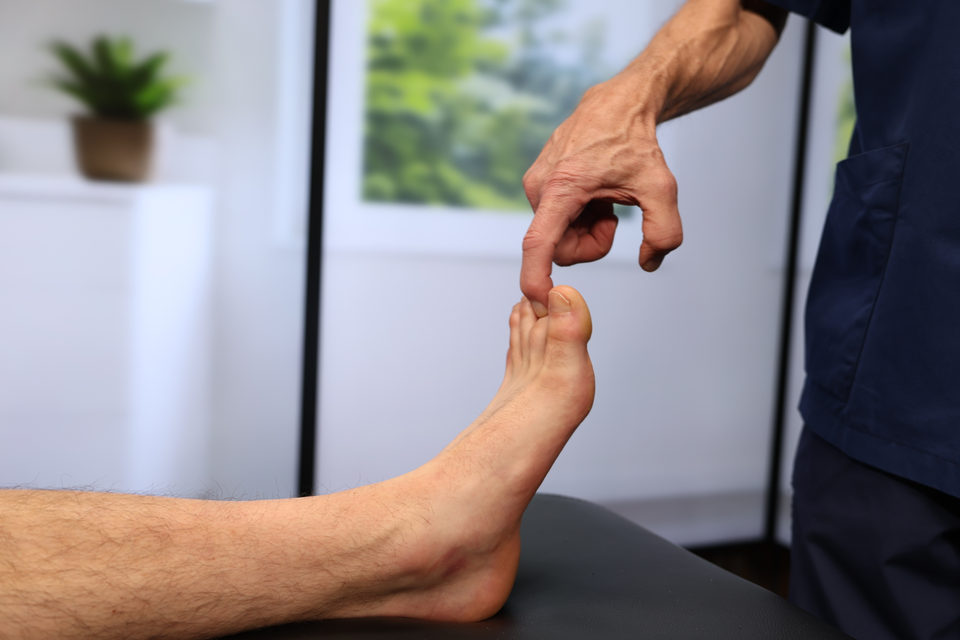
Toe extension
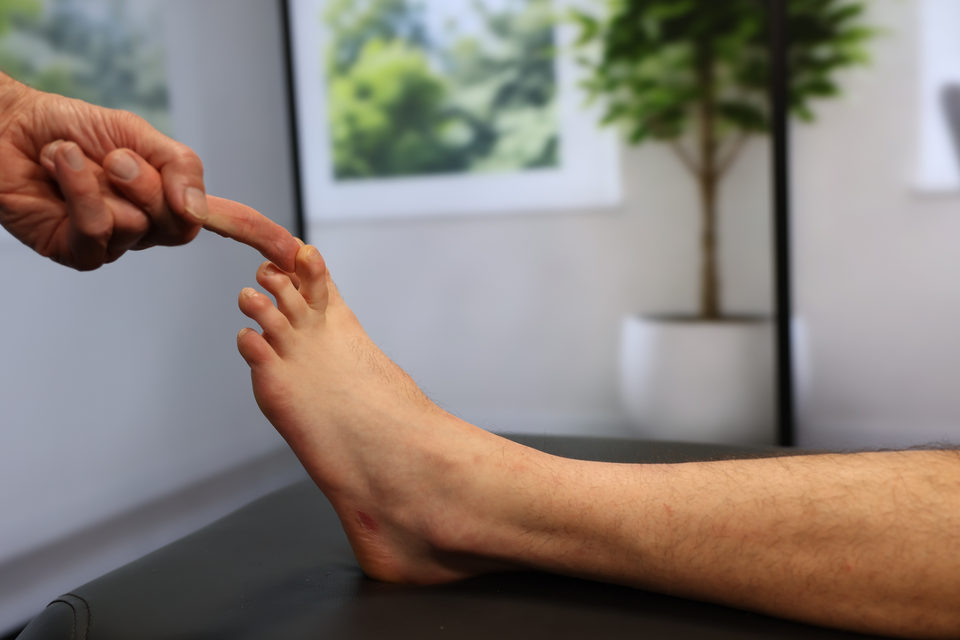
Patient lying on their back. The examiner extends the 2nd toe. Repeat for the 3rd–5th toes.
Isometric movements
- Assess Test in a mid-joint position so that capsules and ligaments are not stretched unnecessarily and do not interfere with the assessment of muscle strength. This is in line with the principles of isometric testing, where the goal is to load contractile structures without provoking inert tissue. The mid-position minimizes stretch on capsules and ligaments so that pain and loss of strength can be attributed to muscle/tendon and not inert tissue. This increases the test's specificity for contractile structures. Stabilize the lower leg well so that the movement is isolated to the correct muscle group. Record pain, strength, asymmetry, and the quality of the contraction.
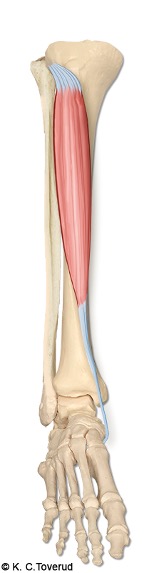
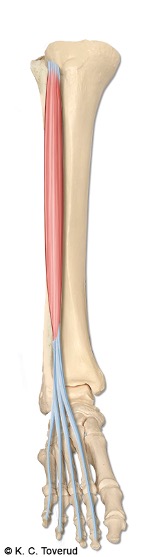
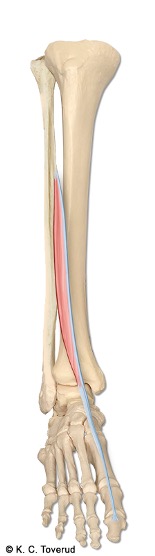
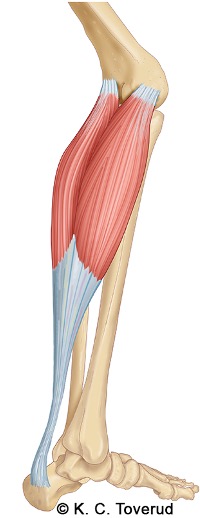
- Consider pain and discomfort with dorsiflexion (tibialis anterior tendinopathy), plantarflexion (Achilles tendinopathy), inversion (tibialis posterior tendinopathy), eversion (peroneus tendinopathy).
Dorsiflexion
Dorsiflexion
Dorsiflexion ankle
Plantar flexion
Ankle plantarflexion
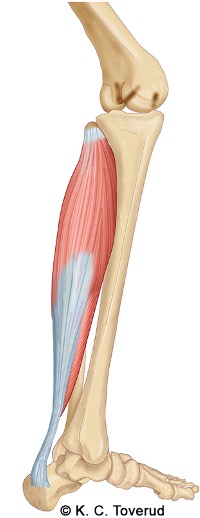
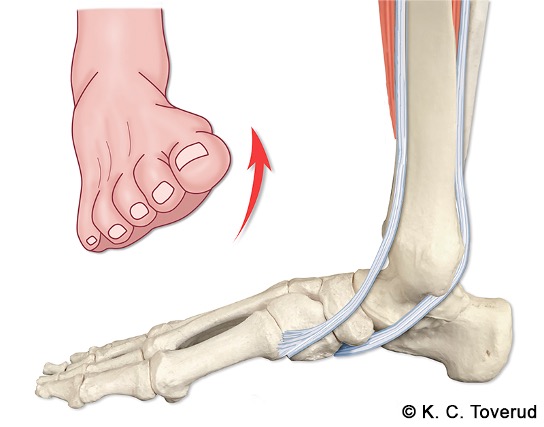
Inversion
Forefoot inversion
Dorsiflexion
Dorsiflexion
Dorsiflexion ankle
Big toe flexion
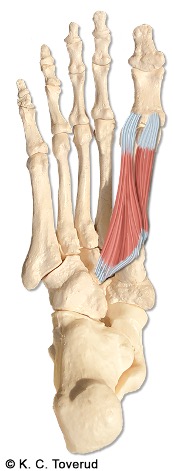
M. flexor hallucis brevis
(N. plantaris medialis, L4-S1)
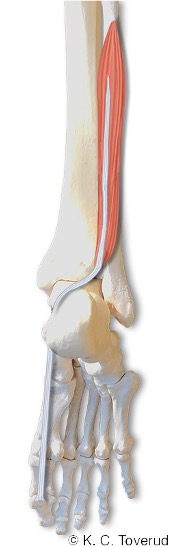
M. flexor hallucis longus
(N. tibialis, L5-S2)
Big toe extension
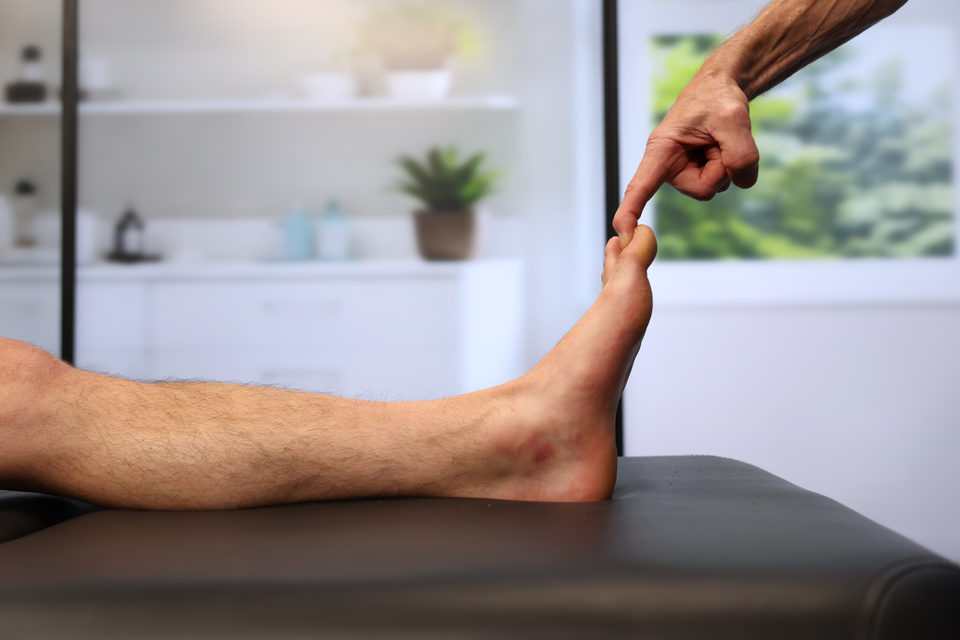
Big toe extension: Muscles and nerves
Toe flexion
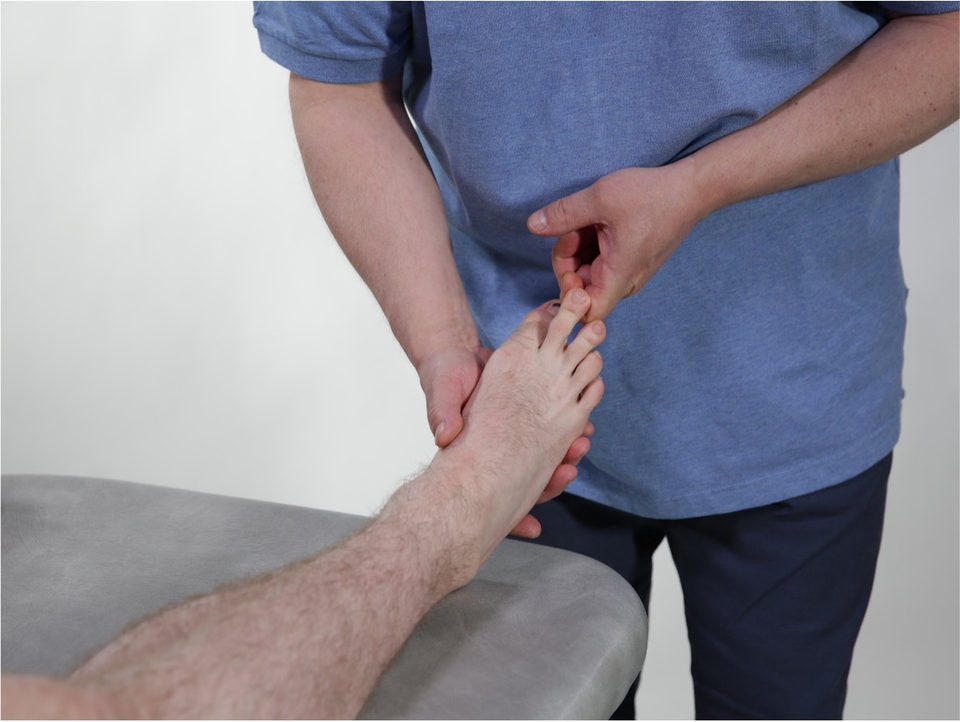
Toe flexion: Muscles and nerves
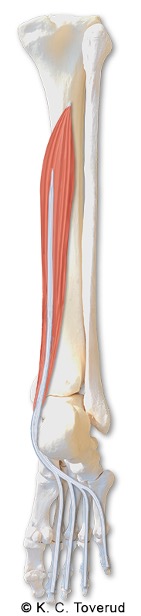
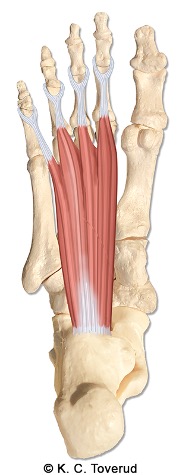
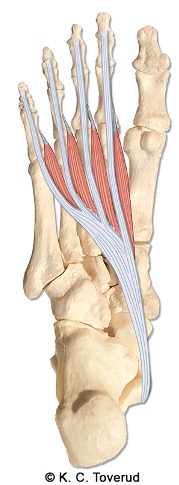
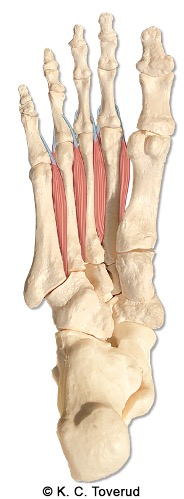
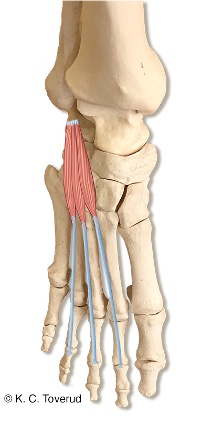
Toe extension
Toe extension: Muscles and nerves
Palpation
- Assess to palpate systematically. Start with palpation of the calf and proceed with the Achilles tendon, malleoli, joint lines, dorsum of the foot, medial/lateral structures and toes. Use both flat fingers (for swelling, warmth, fluid) and pointed palpation (for tendon attachments and small structures). Interpret the findings in light of previous trauma, load history, and gait pattern. Consider the pulse in the dorsalis pedis artery and posterior tibial artery as part of an overall assessment of circulation.
- Consider tenderness to palpation in the calf muscles (especially the medial head of the gastrocnemius where partial ruptures may be present). Assess whether there is hydrops in the ankle joint (swelling is most visible and palpable in the anterior joint line).
Palpation of the calf muscles
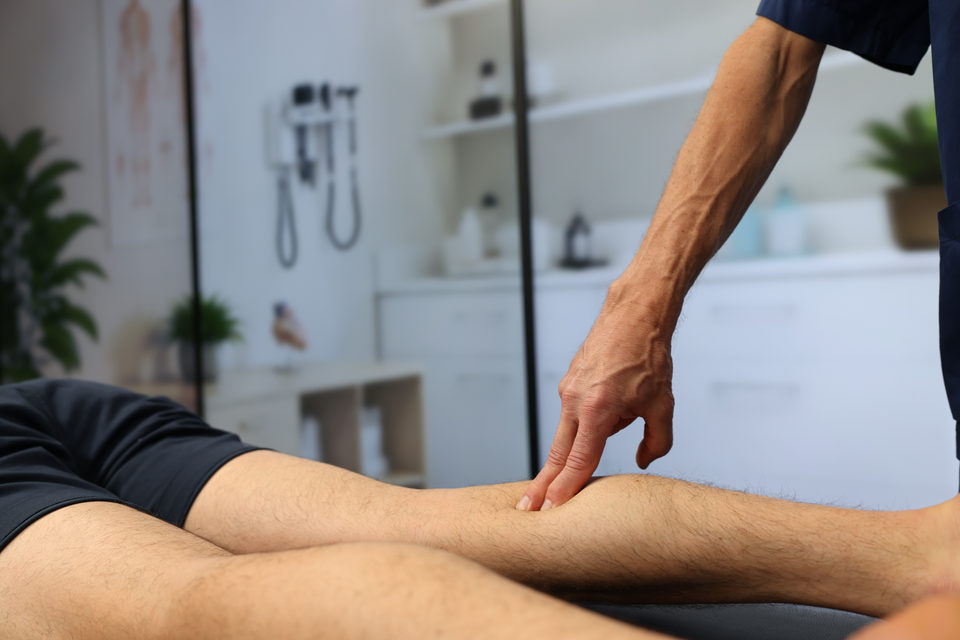
Palpate for tenderness in the muscle belly. Pay particular attention to the medial head of the gastrocnemius. Small ruptures in the muscle belly after overuse or trauma usually occur here.
Tennis leg
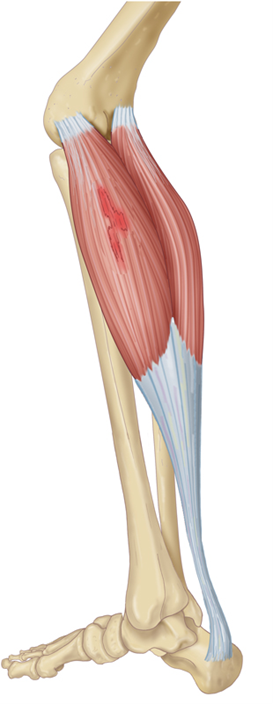
In small ruptures in the muscle belly, slight swelling and bluish discoloration from bleeding may be observed. On palpation, there may be pain and often a small palpable depression in the muscle belly.
Hydrops
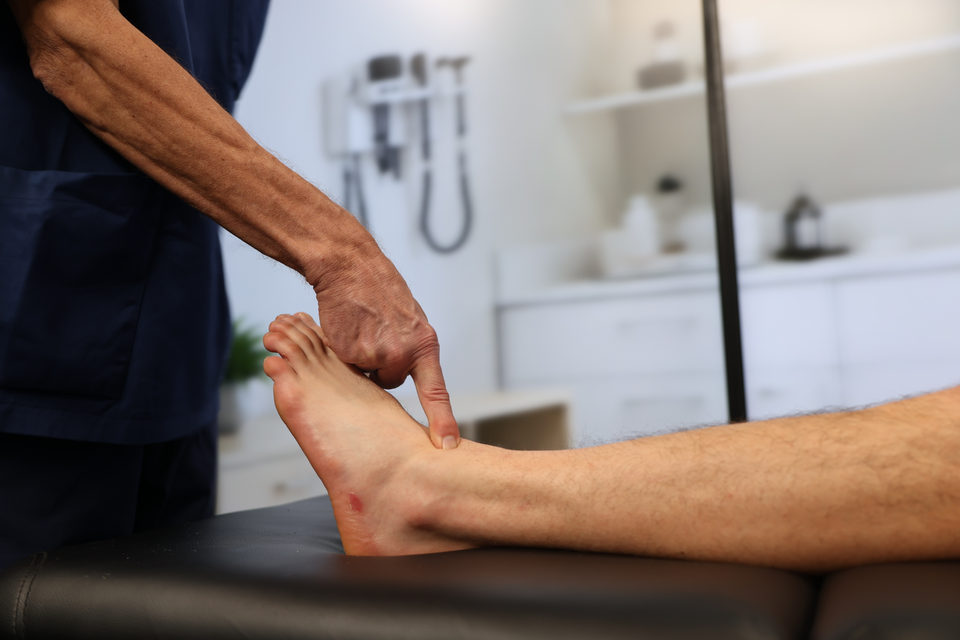
Joint swelling is observed and can be palpated best at the anterior joint line of the talocrural joint. During functional examination of movement in an ankle joint with hydrops, one will find reduced range of motion for flexion and extension.
A. dorsalis pedis
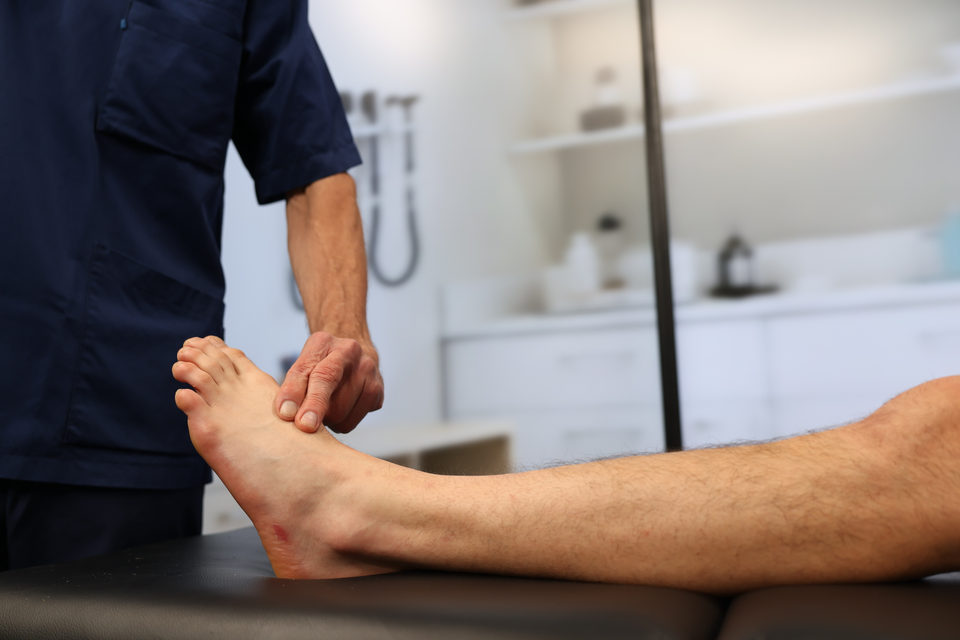
Palpation of the pulse in the a. dorsalis pedis on the dorsum of the foot. Palpate the pulse lateral to the tendon of the m. extensor hallucis longus.
A. tibialis posterior
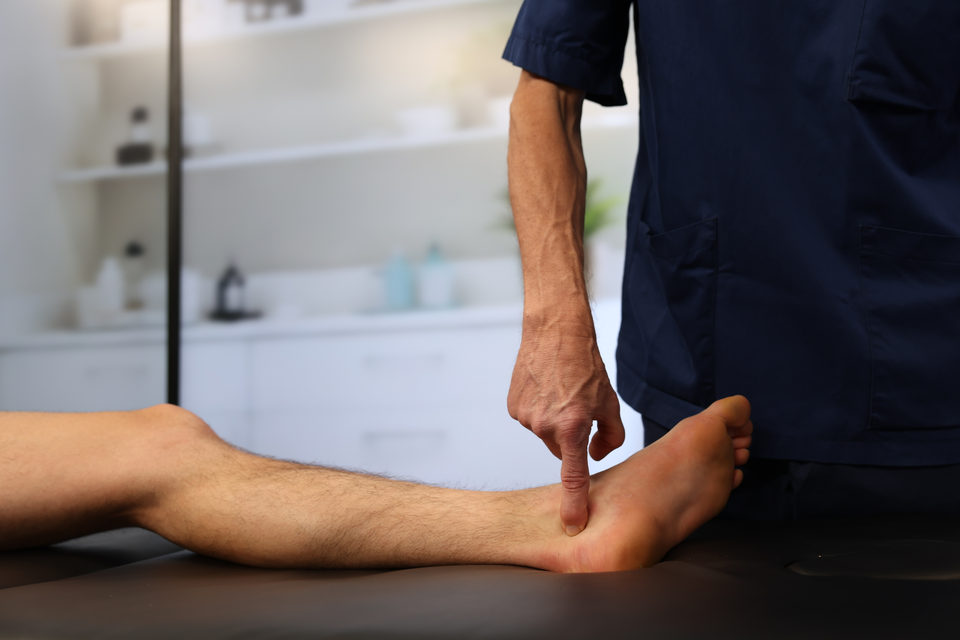
Palpation of the pulse in the a. tibialis posterior behind the medial malleolus. Palpate the pulse behind the medial malleolus.
Assessment of clinical presentation based on functional examination
Ankle injuries are the most common cause of ankle pain. Ligament injuries may lead to chronic instability and subsequently to osteoarthritis, so this possibility should be considered in younger patients with a history of ligament injury. Ankle osteoarthritis causes reduced range of motion, weight-bearing pain, joint swelling and a capsular pattern in which plantar flexion is more restricted than dorsiflexion. A non-capsular pattern may be caused by a loose body in the ankle joint. Chronic lateral ligament injury often presents with normal range of motion and negative isometric tests. Patients frequently report a sense of instability; this should be assessed with the anterior drawer and talar tilt tests.
Pain in the front part of the ankle joint can be caused by periostitis in the distal part of the tibia; patients will report pain with passive dorsiflexion. Pain in the front part of the ankle joint can also be caused by tenosynovitis in the toe extensors; in that case, one will find pain with isometric dorsiflexion of the toes and often crepitation and swelling over the tendon sheaths of the toe extensors.
Pain medially in the ankle joint can be caused by injury to the deltoid ligament; passive eversion and plantarflexion in the ankle joint can then trigger pain. Pain medially can also be caused by tendinopathy in the tibialis posterior muscle, isometric plantarflexion and inversion will then be painful.
Pain posteriorly in the ankle joint can be caused by Achilles tendinopathy. You will then find pain when walking on your toes, increased warmth over the Achilles, swelling, and pain on palpation over the tendon.
In the case of an acute injury with suspicion of Achilles rupture, there will be decreased strength for toe walking, often a palpable gap in the muscle/tendon junction, and a positive Thompson test.
In the heel region and under the calcaneus, pain can be caused by plantar fasciitis. Patients report pain under the heel when walking and under load. Most often, the functional examination of the ankle and foot is normal in this condition, but suspicion of plantar fasciitis based on the medical history can be confirmed by extreme tenderness on palpation at the attachment of the plantar fascia medially on the calcaneus.
Final competence
- Perform relevant clinical examination in a skilled and gentle manner
- Interpret clinical findings and be able to establish tentative diagnoses
- Suggest referral and treatment
Last updated 05.10.2026