
Video demonstration
Inspection
- Assess the patient from the back, front, and side to get a comprehensive picture of neck and head posture. Assess whether there are postural deviations, muscle atrophy, and asymmetry. It can be difficult to determine what is considered normal body posture and which deviations may be clinically relevant. Poor posture can involve forward head, protracted shoulders, reduced or increased cervical lordosis, increased thoracic kyphosis, straightened lumbar lordosis, and backward pelvic tilt. Such posture can lead to increased muscular tension and reduced range of motion, and in some cases thereby predispose to pain in the jaw, neck, shoulders, and lower back.
- Consider about whether there are clinical signs of poor posture. Postural deviations must always be considered in relation to function, pain, and muscular status. Whether the cervical lordosis increases or decreases is determined by an interaction between head position, muscle balance, thoracic posture, pelvic position, and neuromuscular control. With increased lordosis, one may find increased tension in the suboccipital muscles, in m. levator scapulae, and in the upper part of m. trapezius, and weakness in the deep neck flexors (m. longus colli/capitis). With reduced lordosis, often increased tension in m. sternocleidomastoideus and in the infrahyoid muscles and weakness in the deep neck extensors (local stabilizers such as mm. multifidi cervicis, mm. semispinalis) cervicis and the suboccipital muscles mm. rectus capitis posterior major/minor and mm. obliquus capitis superior/inferior.
From the back

On inspection from behind, one notes whether the patient stands with the head rotated or with lateral tilt.
From the front

On inspection from the front, one looks at the orientation of the head in relation to the body axis and shoulders.
Topographic anatomy
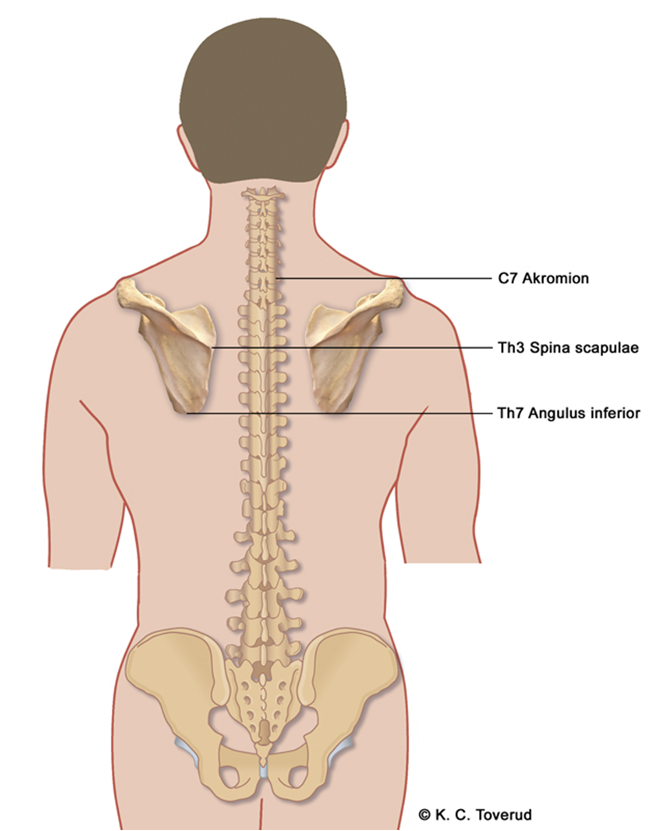
- C7 Acromion
- Th3 Spine of scapula
- TH7 Inferior angle
Take a position on the anatomical landmarks that help identify the spinous processes C7, Th3, and Th7.
A straight line from the acromion towards the spine meets the C7 level. A straight line from the scapular spine towards the spine meets the Th3 level. A straight line from the inferior angle of the scapula towards the spine meets the Th7 level.
Side

During side-view inspection, one looks for the cervical lordosis and whether the patient stands with a forward head position. Forward head posture can in the upper cervical spine (C0–C2) lead to increased lordosis (extension) and in the lower cervical spine (C3–C7) reduced cervical lordosis (straight alignment). Overall, the neck curve can appear flattened. When inspection shows forward head posture with flattened lower cervical lordosis and compensatory increased upper cervical extension, this is consistent with overactive sternocleidomastoid and infrahyoid muscles as well as reduced deep posterior neck stability.
Body posture
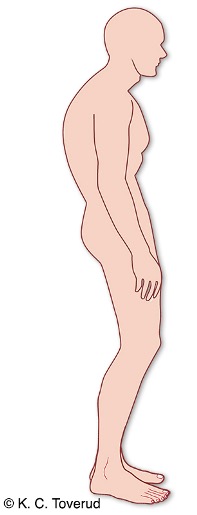
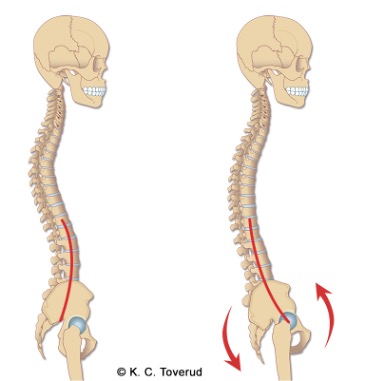
- Forward head position
- Increased or reduced cervical lordosis
- Increased thoracic kyphosis
- Posterior pelvic tilt
Seen from the side, this posture will be characterized by increased thoracic kyphosis, anterior positioning of the shoulder girdle, protracted shoulders (shoulders forward and up), increased flexion of the cervicothoracic junction, straightened or in some cases increased cervical lordosis, and increased extension of the occiput on the atlas. The center of gravity of the head is then shifted forward, which in turn causes the neck muscles, especially the suboccipital muscles, to work with constant tension (E H Julsvoll (ed.), Temporomandibular Dysfunction. Theory, examination, treatment. Cappelen Damm Akademisk 2018).
Active movements
- Assess about whether there is normal range of motion and whether active movements trigger pain.
- Consider about whether there is symmetrical reduced mobility with pain at the end points of the range of motion → sign of spondylosis. With only reduced mobility in one direction with radiation to the arm → sign of nerve root involvement.
Extension

At maximum extension, the nose and forehead are near the horizontal plane.
Flexion

At maximum flexion, there is a maximum of two finger widths between the chin and chest.
Rotation

At maximum rotation, the nose should point over the shoulder.
Lateral bending

Note how far the ear comes down toward the shoulder. Make sure the patient does not lift the shoulder up, so that it does not create a falsely large lateral bend.
Active elevation of the shoulder girdle
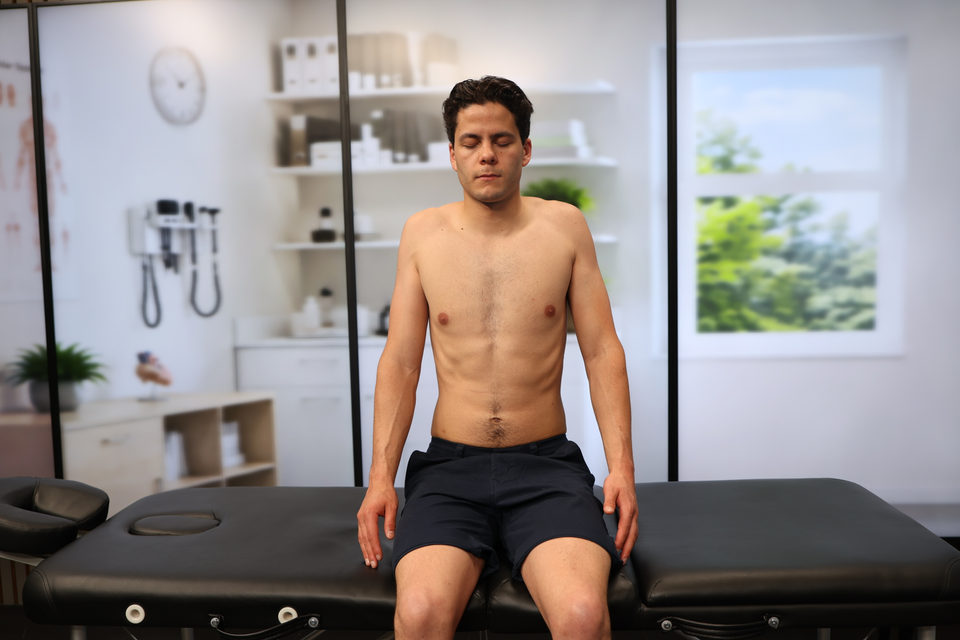
Symmetrical lifting of both shoulder girdles
Active movement of head and neck
- Sum of mobility in the joints between the base of the skull-atlas (C0-C1, yes joint), atlas-axis (C1-C2, no joint) and the lower part of the neck (C2-C7) which depends on
- Degree of flexibility in the intervertebral discs
- Degree of wear in the intervertebral joints
- Degree of flexibility in ligaments and joint capsules
Passive movements
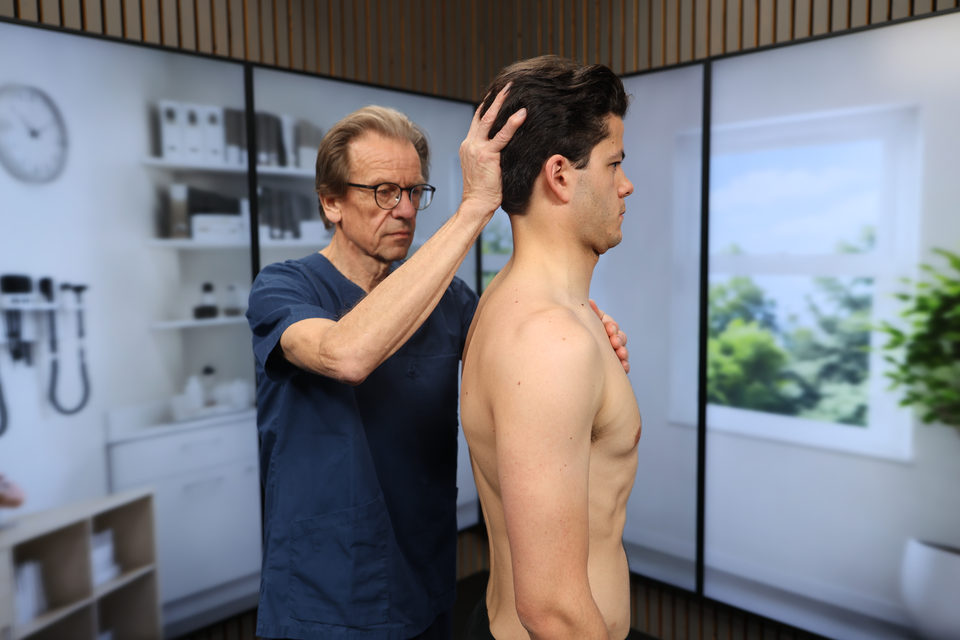
- Assess In standing or sitting position, pain, range of motion, and end-feel. Stabilize the patient's shoulders so that the movement is pure cervical movement.
- Consider about whether there is a normal elastic end-feel. During passive movement, non-contractile tissue such as the joint capsule, ligaments, and facet joints are tested. It is important to differentiate between muscular pain (active movement/isometric) and joint-related pain (passive movement). With reduced mobility and pain at the end-point of the range of motion → signs of spondylosis. With reduced mobility and pain in one direction → signs of radiculopathy.
Extension 85°
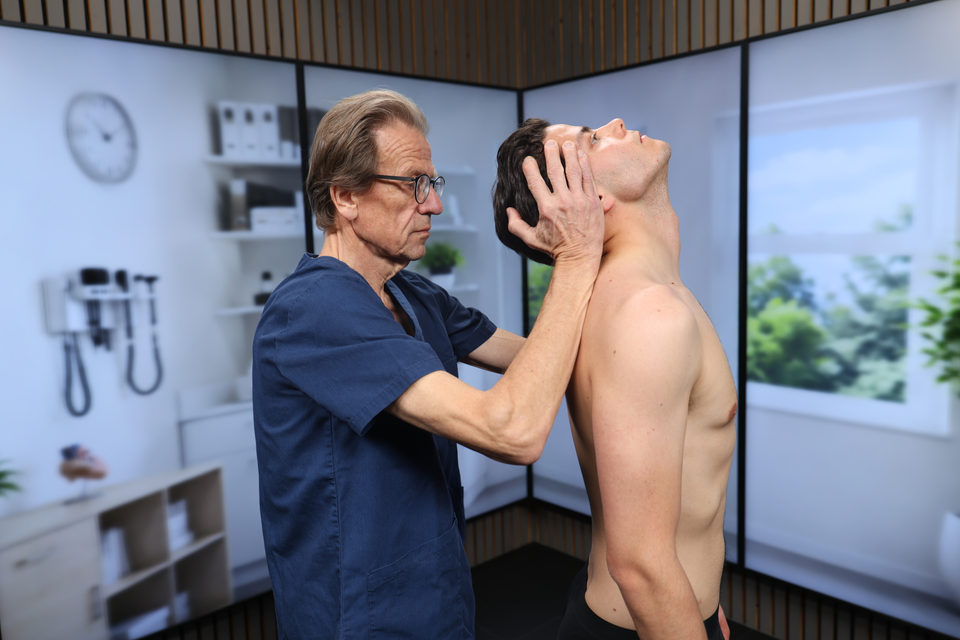
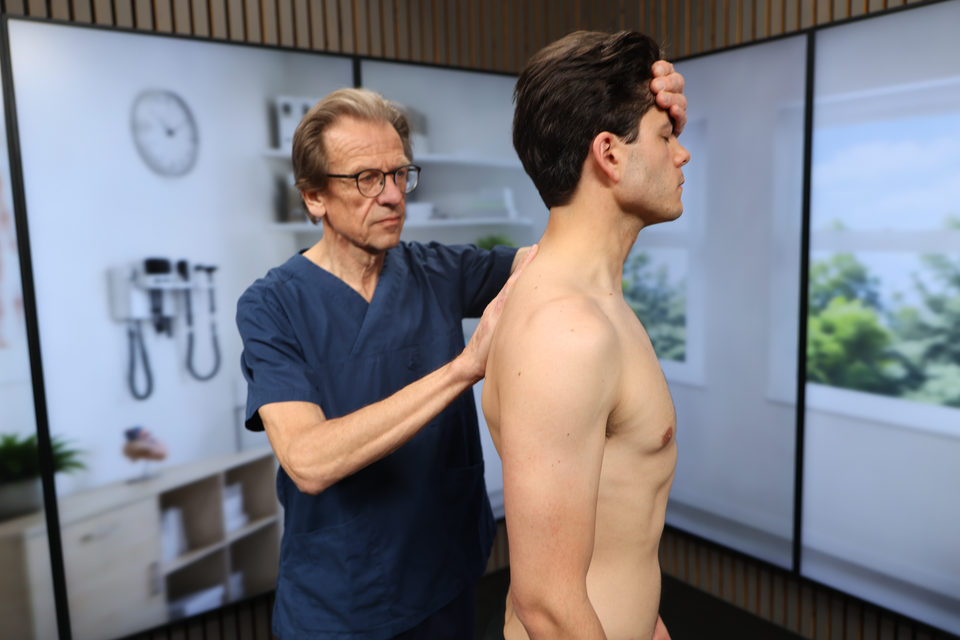
Examining by gripping the head over the temples with both hands; elbows supported on the shoulder arch; bring the head into full extension. Pain at the end-point may indicate spondylosis. Radiation into the arm may indicate radiculopathy.
Flexion 45-50°
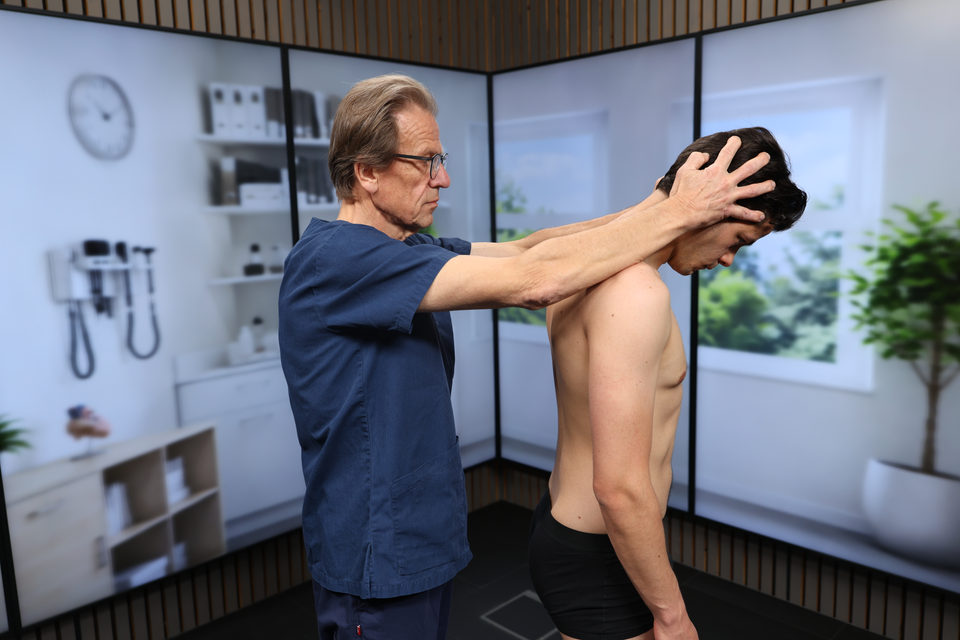
Move the neck gently in passive flexion without pressing. Assess range of motion and pain. Stop if there are electric shock-like sensations down the spine or into the arms or legs; this may be Lhermitte's sign and indicate spinal cord involvement. Radiating arm pain may indicate nerve root involvement.
Rotation 80°

Stabilize the shoulder girdle with the elbow; bring the neck into full rotation. Asymmetric range of motion may point to facet joint irritation/herniated disc. Radiation into the arm may indicate radiculopathy.
Side bend 40°

Stabilize the shoulder; hand on the side of the head; bring the neck into passive side bending. Pain and asymmetry may point to facet joint osteoarthritis or myalgia. Radiation into the arm may indicate radiculopathy.
Degenerative neck, cervical spondylosis
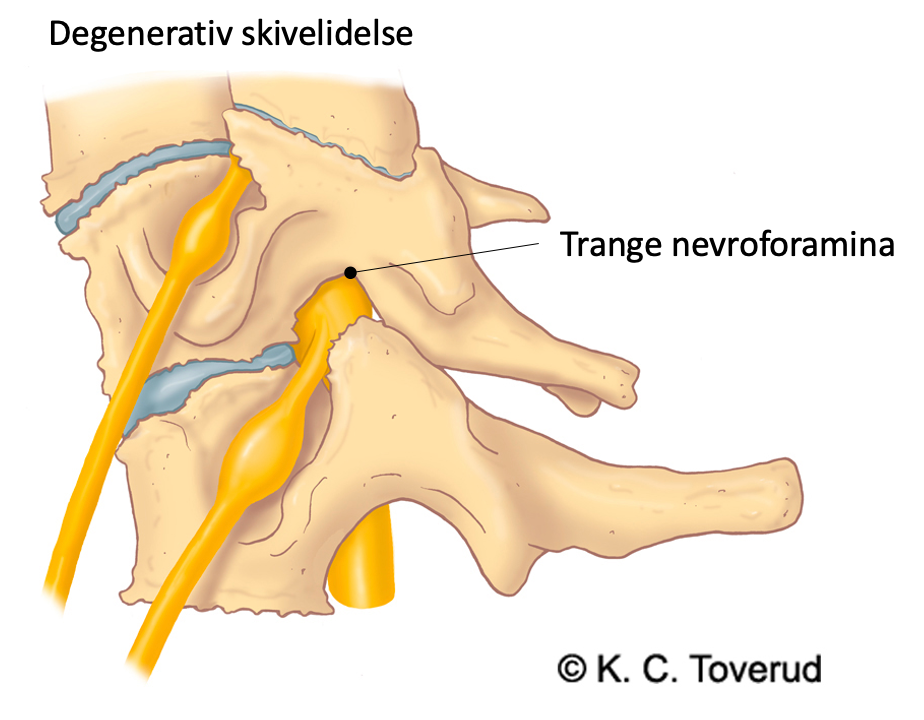
Neck, skeleton
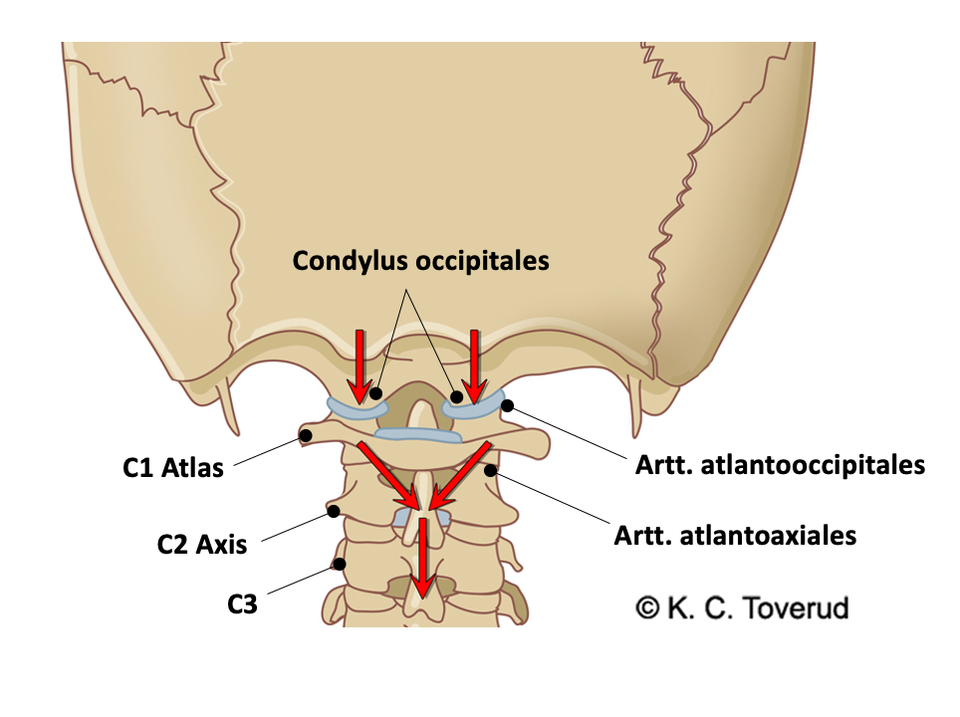
The weight of the head (5 kg) and the contraction force of the neck muscles are distributed across the artt. atlantooccipitales, transferred to the artt. atlantoaxiales and from there to the C2-C3 intervertebral disc.
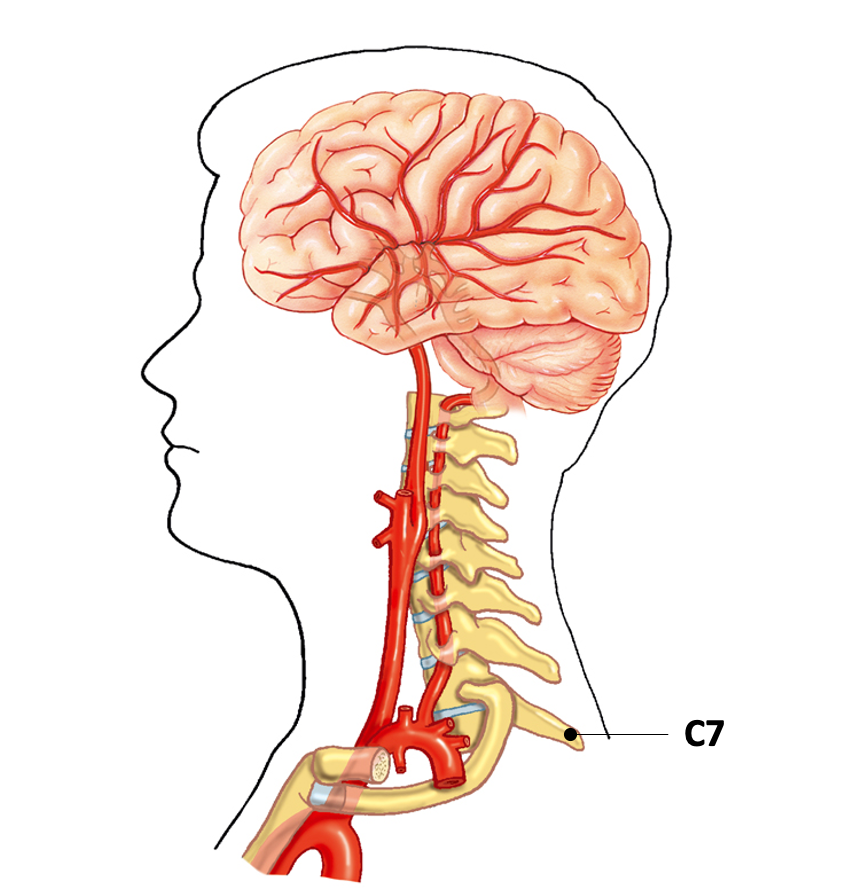
C7 is called the vertebra prominens. The arteria vertebralis branches from the a. subclavia and then passes through the transverse processes from C6 to C1.
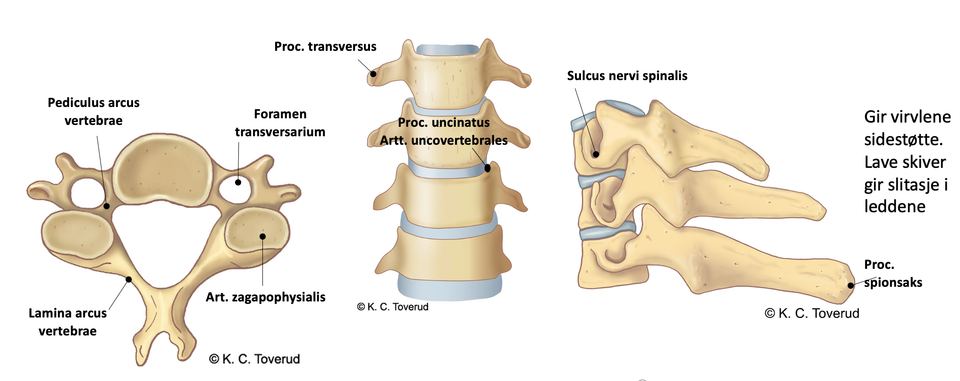
Cervical vertebrae C3-C7, uncovertebral joints and facet joints
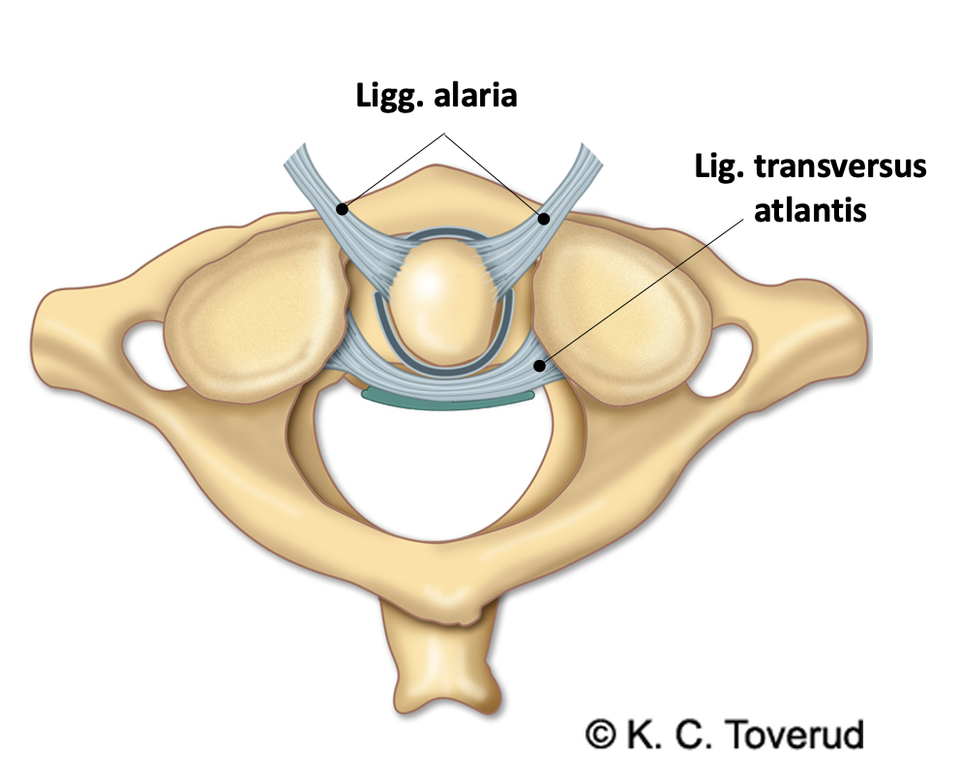
Alar ligaments
Isometric movements
- Assess muscle strength in isometric contractions against resistance.
- Consider whether muscle strength is normal or reduced → neurogenic injury.
Flexion (C1-C2)
Neck flexion, superficial muscles
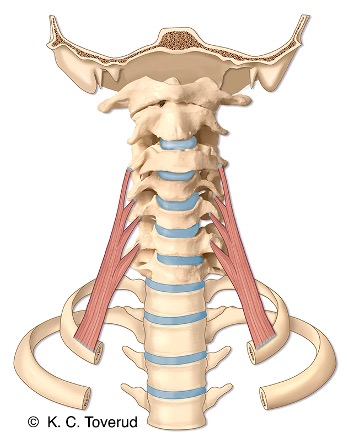
M. scalenus anterior
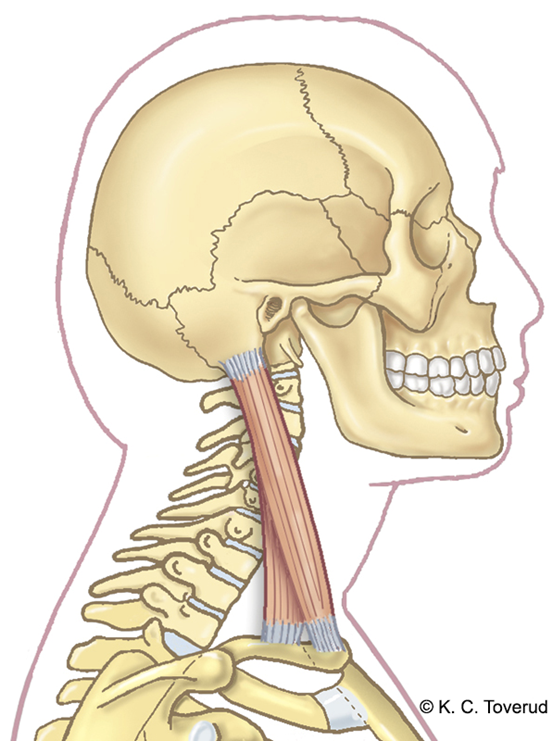
M. sternocleidomastoideus
Neck flexion, deep muscles
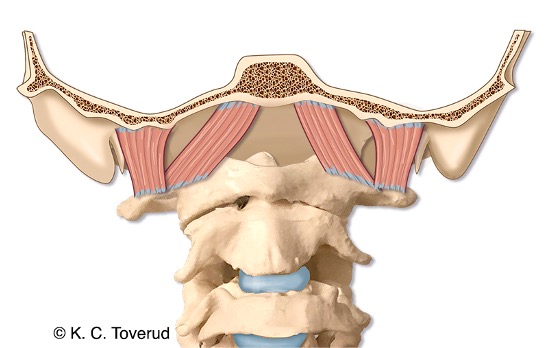
M. longus capitis and M. longus colli
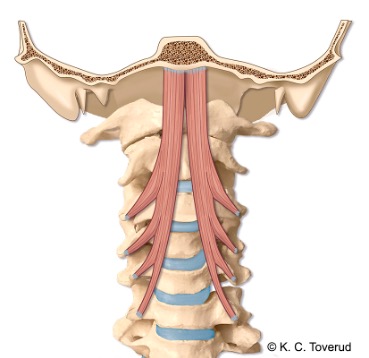
M. longus capitis
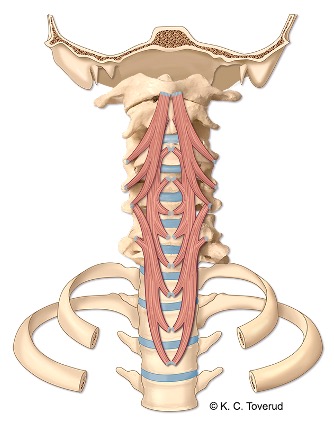
M. longus colli
Extension (C1-C2)
Neck extension, superficial muscles
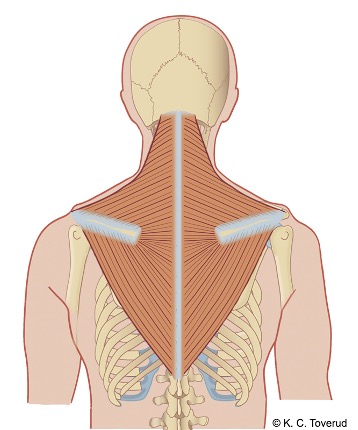
M. trapezius
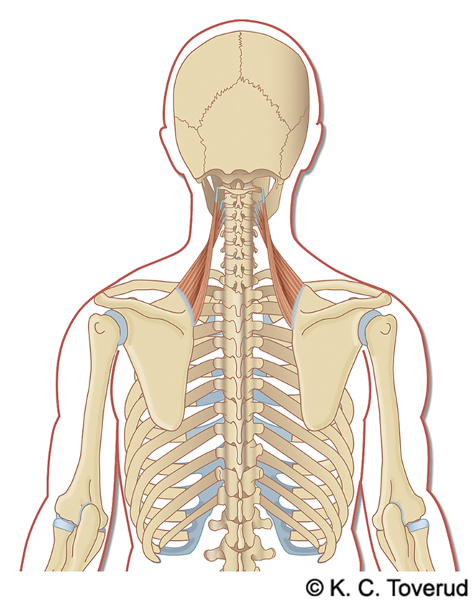
M. levator scapulae
M. spenius capitis et cervicis
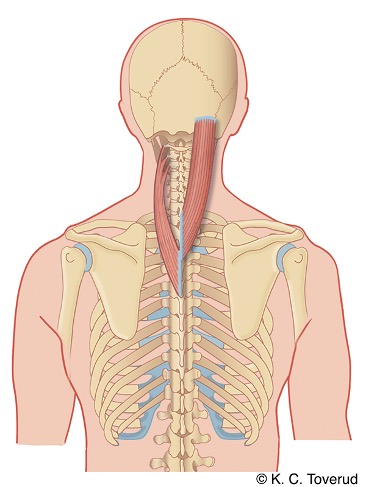
M. longissimus capitis and M. longissimus cervicis
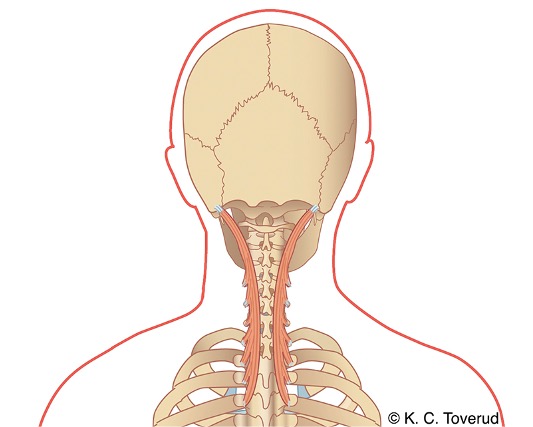
M. longissimus capitis
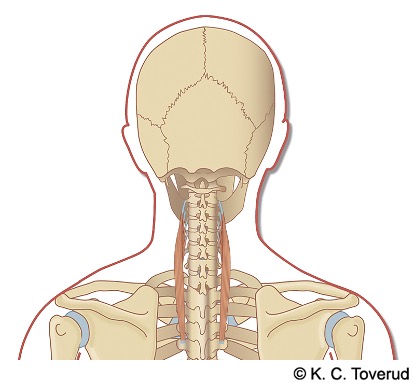
M. longissimus cervicis
M. spinalis capitis and M. spinalis cervicis
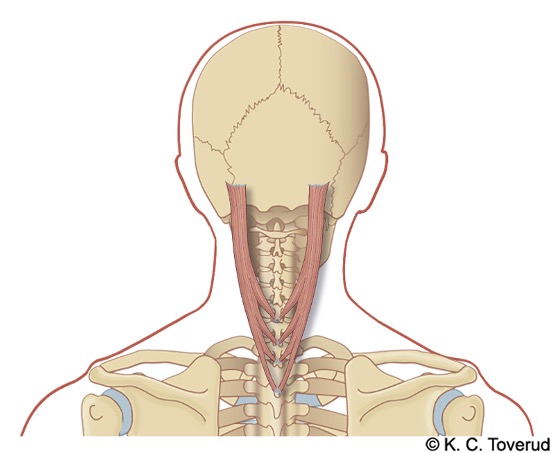
M. spinalis capitis
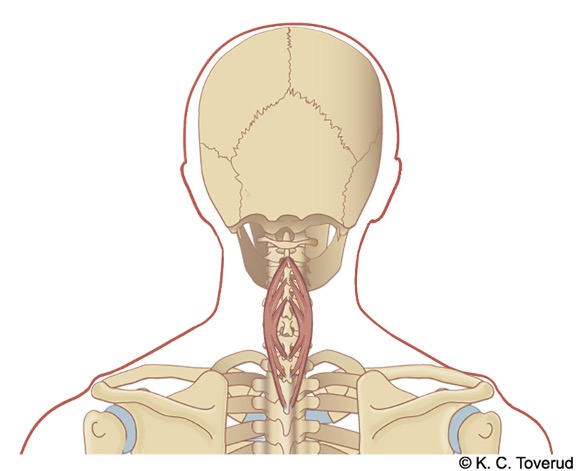
M. spinalis cervicis
M. iliocostalis cervicis
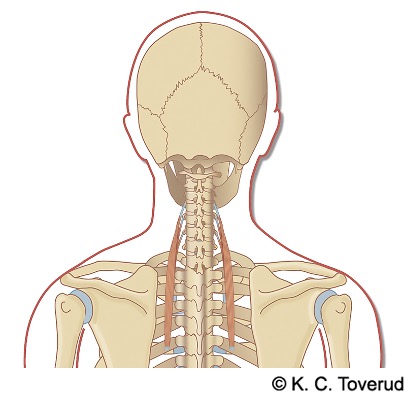
Mm. suboccipitales and M. semispinalis capitis et cervicis
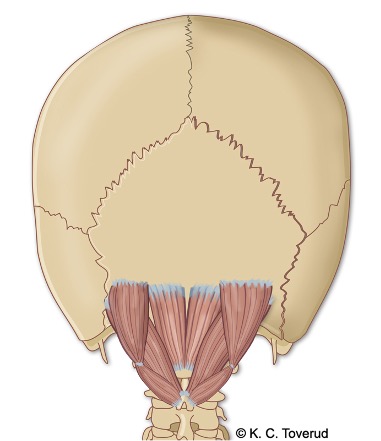
Mm. suboccipitales
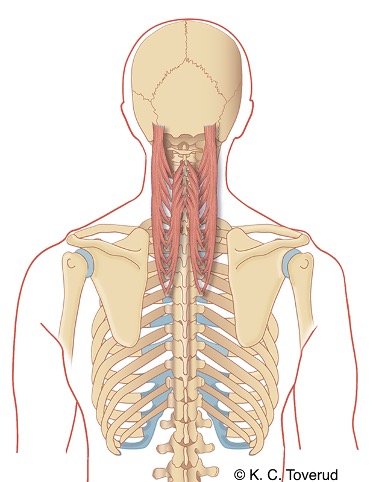
M. semispinalis capitis et cervicis
Rotation (C1-C2)
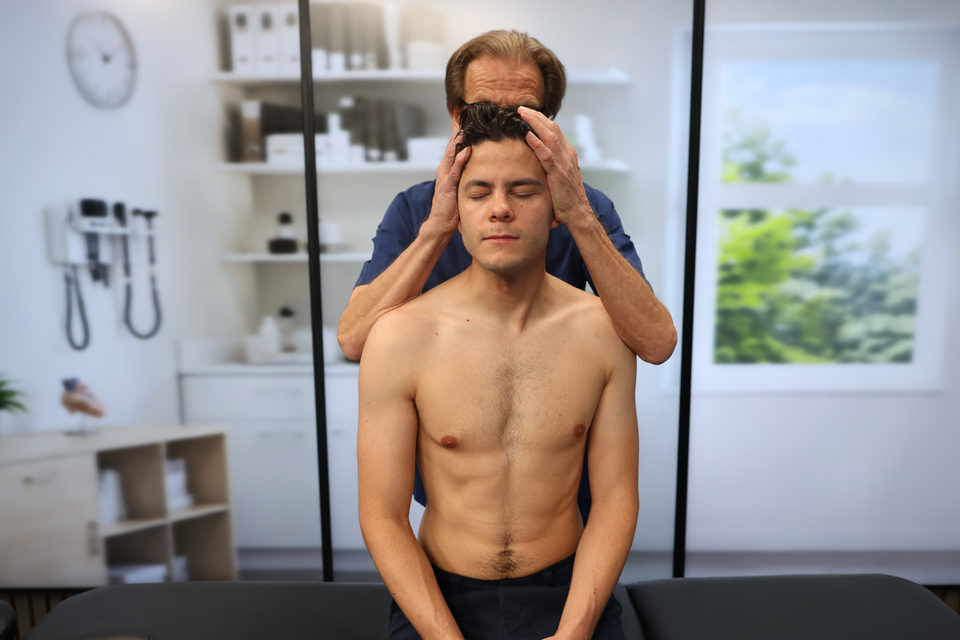
Neck rotation, superficial muscles
M. sternocleidomastoideus
M. trapezius
M. spenius capitis et cervicis and M. longissimus capitis et cervicis
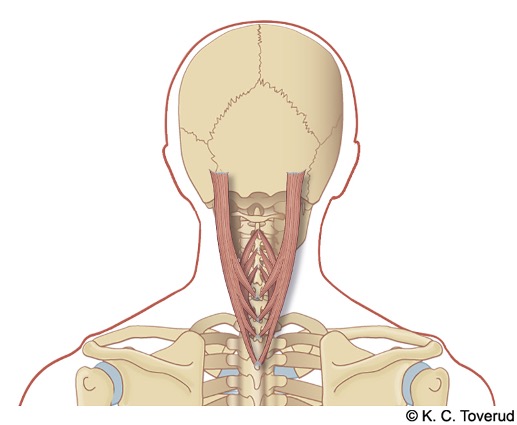
M. spenius capitis et cervicis
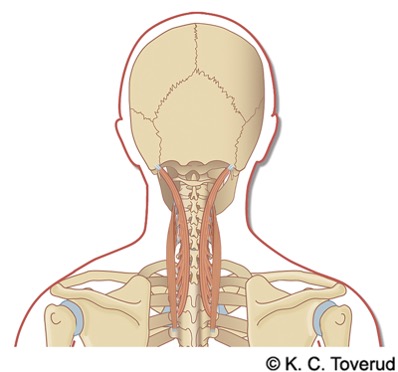
M. longissimus capitis et cervicis
M. scalenus anterior and M. levator scapula
M. scalenus anterior
M. levator scapula
M. iliocostalis cervicis
Neck rotation, deep muscles
M. semispinalis capitis et cervicis
Mm. suboccipitales
Lateral bending (C3)
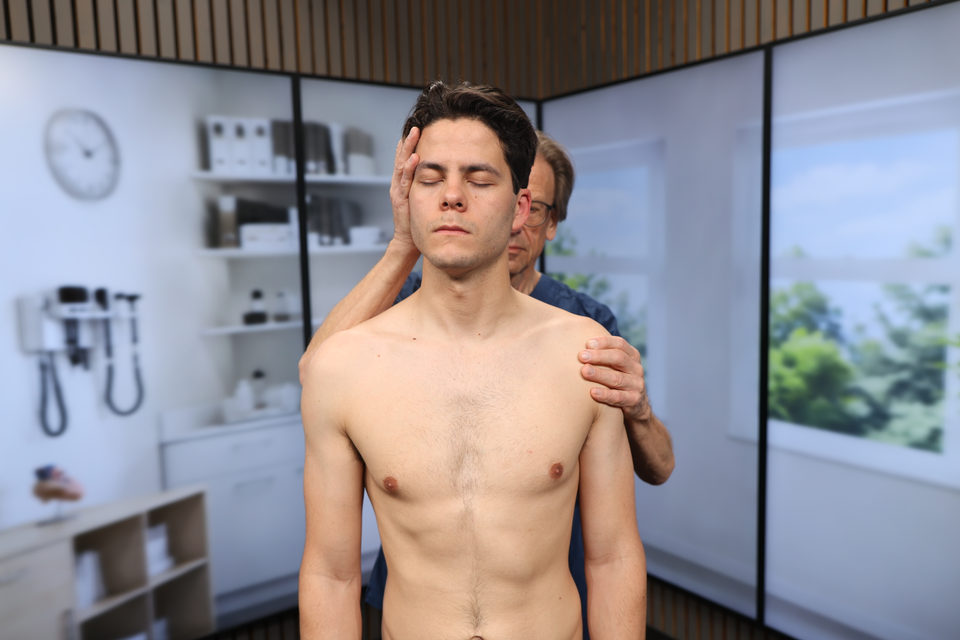
Neck lateral bending, superficial muscles
M. trapezius
M. sternocleidomastoideus
M. spenius capitis et cervicis and M. longissimus capitis et cervicis
M. spenius capitis et cervicis
M. longissimus capitis et cervicis
M. scalenus medius and M. levator scapula
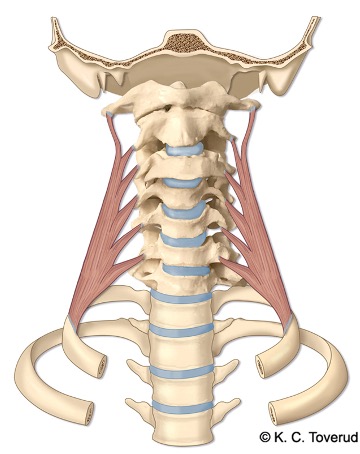
M. scalenus medius
M. levator scapula
M. iliocostalis cervicis
Neck lateral bending, deep muscles
M. semispinalis capitis et cervicis
Mm. suboccipitales
Shoulder girdle elevation (C4)
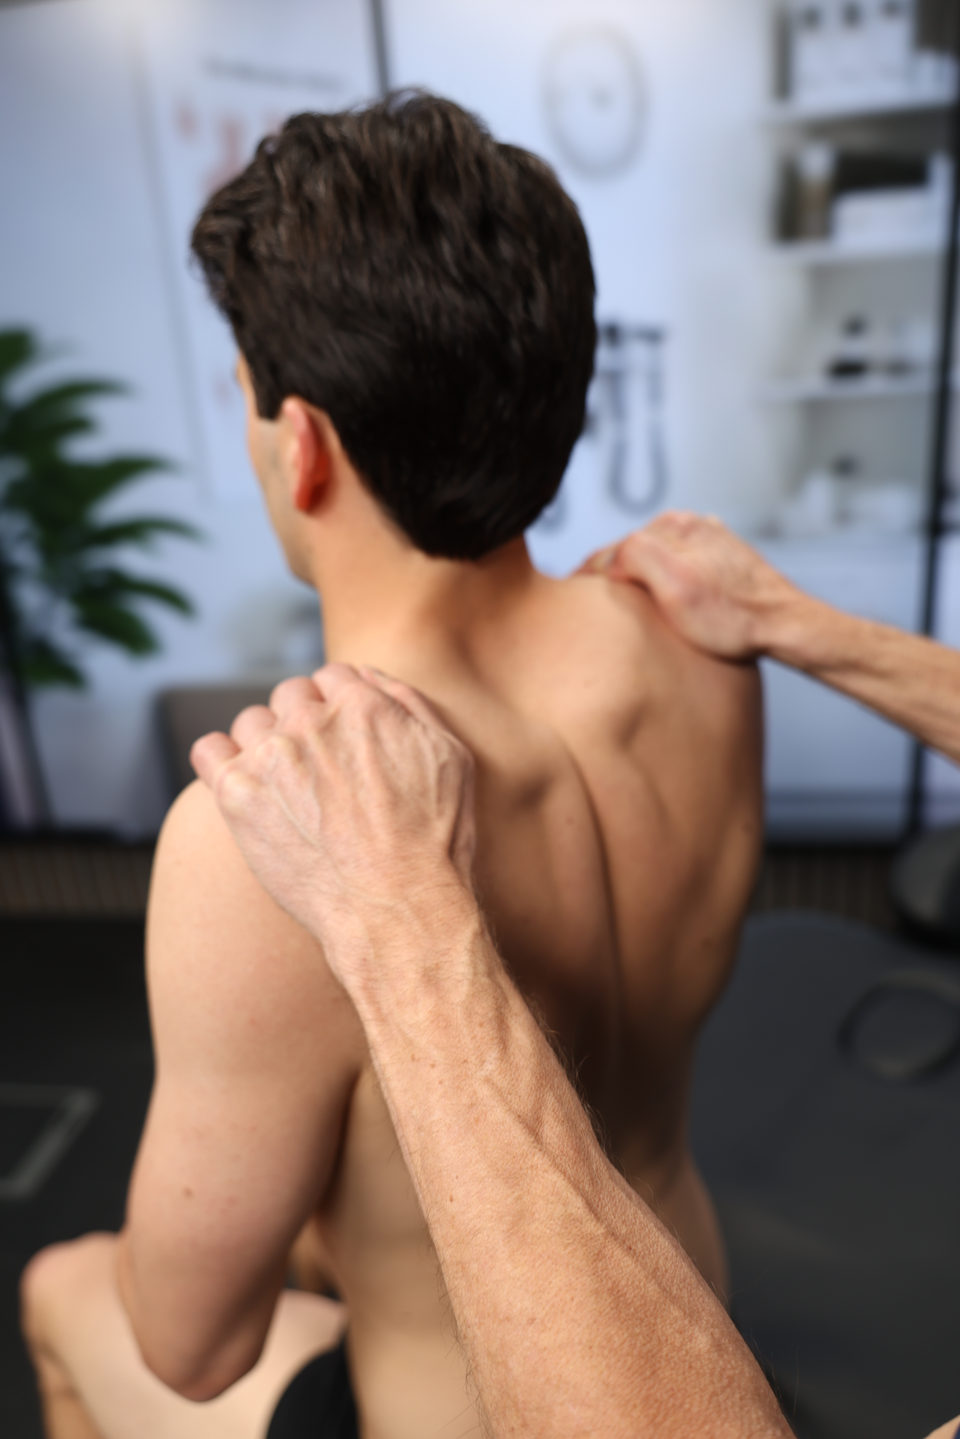
Shoulder girdle elevation, muscles
M. trapezius
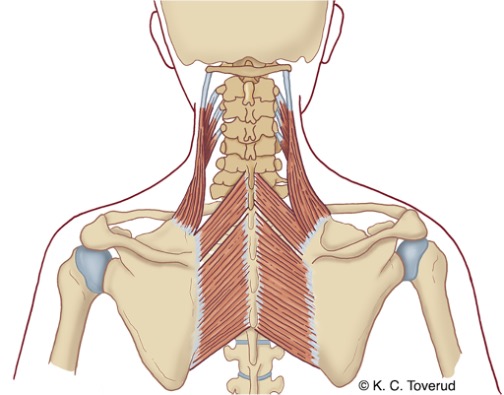
M. levator scapula
M. rhomboideus minor and major
Neck, stability
- Joints and ligaments account for about 20% of the mechanical stability in the neck
- Joints and ligaments are most important for stability at the extreme points of range of motion
- Muscles around the neck provide 80% of the mechanical stability
- The muscles are most important as stabilizers when the neck is in a neutral position and during small ranges of motion
Neck, innervation
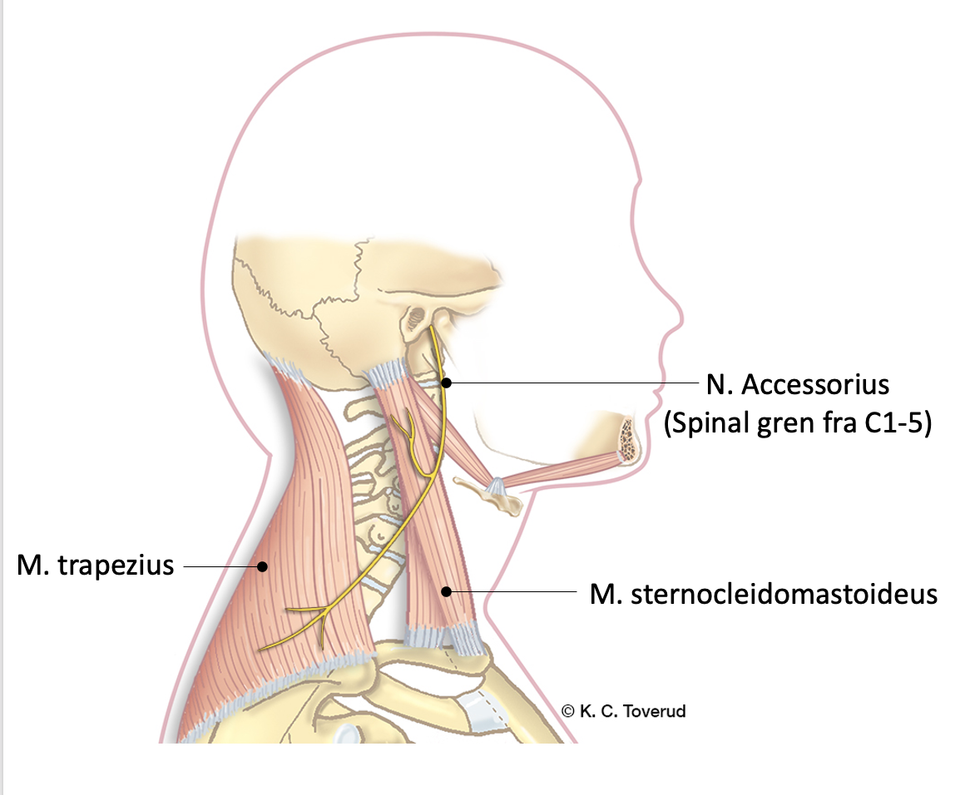
Motor innervation from the 11th cranial nerve
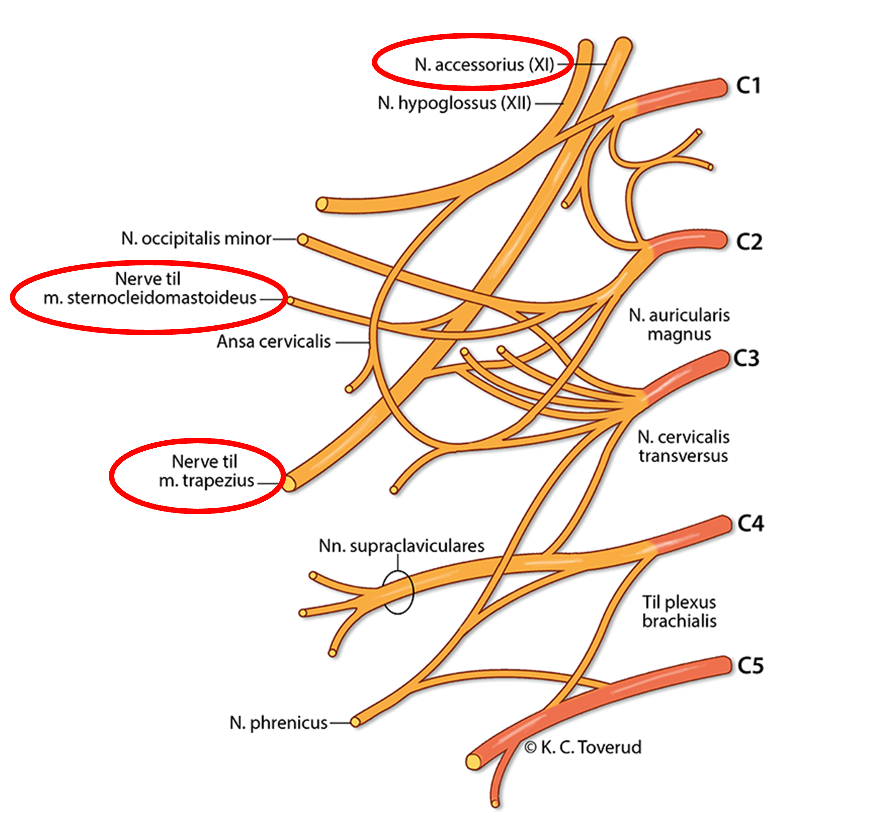
N. accessorius (11th cranial nerve)
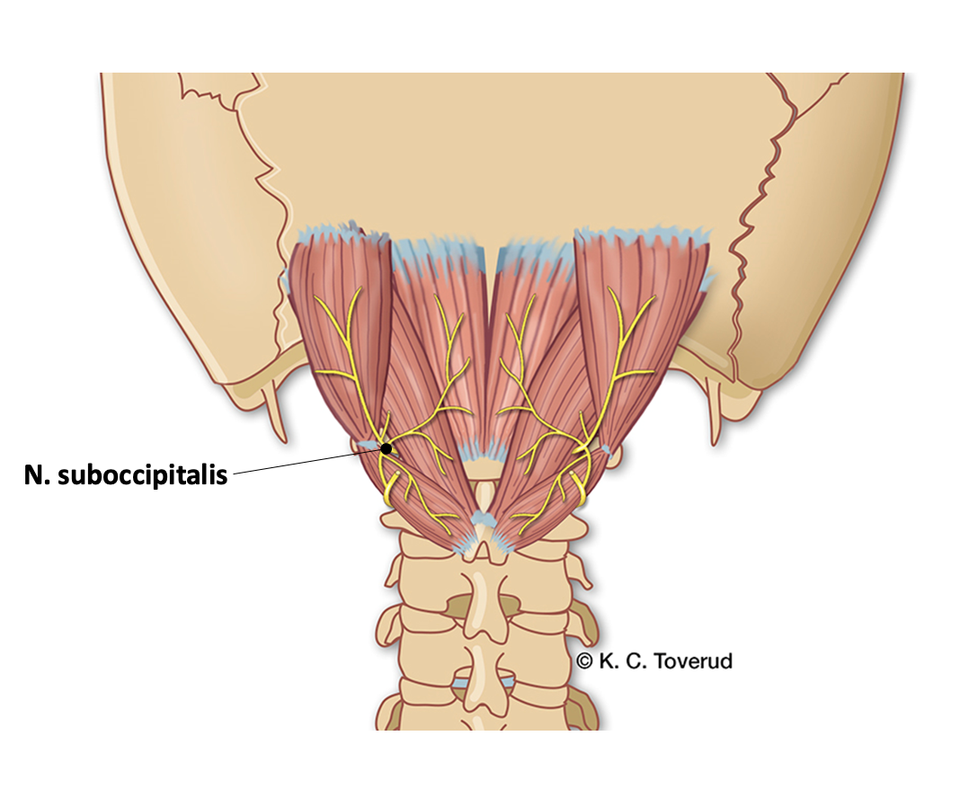
Motor innervation from n. suboccipitalis
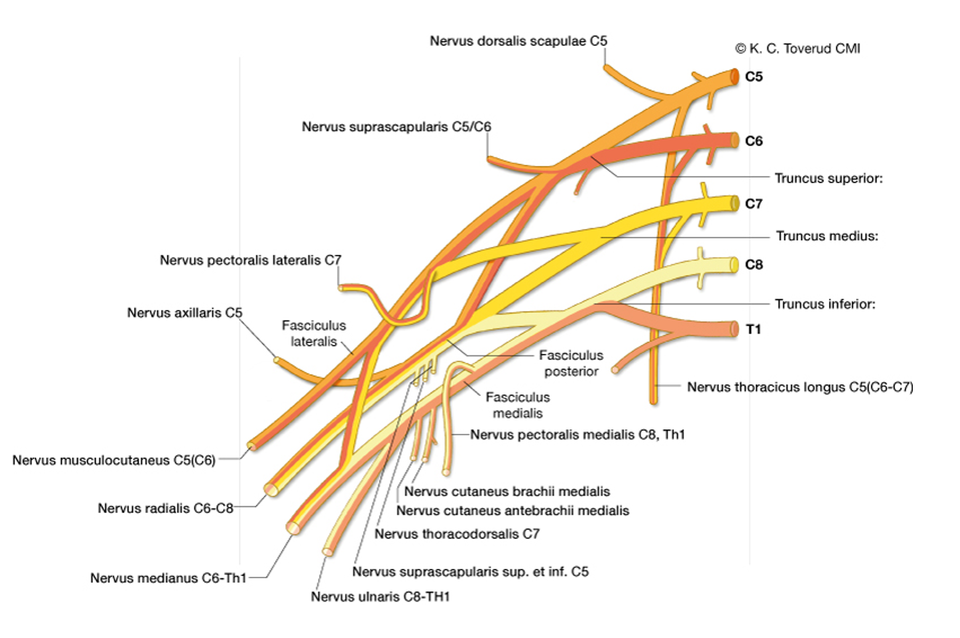
Motor innervation from n. dorsalis scapula
Function, deep neck muscles
- Important for balance
- Afferent information about the position of the head from the cervical muscles is sent to the vestibular nuclei, where it converges with information about head movement from the balance system and the eyes. Important for maintaining an upright posture when the head is turned to the side, as well as hand-eye coordination
- Important for eye movements
- Afferent information is sent from muscles, ligaments, and facet joints in the upper cervical spine to the vestibular nuclei and from there to the muscles that control eye movements
- The cervico-ocular reflex stabilizes the eyes as a response to movements of the head relative to the body
- Pain and dysfunction in the neck muscles
- Can cause headaches, dizziness, visual disturbances, and impair balance
- Other important functions of the deep neck muscles
- Maintain the craniocervical lordosis
- Facilitate the extension movement in the C0-C1 joint
Palpation
- Assess about whether there are localized pains in the muscles. Palpate systematically and assess tensions and pains in the mm. suboccipitales, m. trapezius, m. levator scapulae and m. sternocleidomastoideus. Palpation is unspecific and poorly reproducible. It is not used to make a diagnosis alone, but to identify pain areas, uncover muscular dysfunction, and distinguish between local and generalized pain.
- Consider about whether there are trigger points in the muscles and whether palpation elicits referred pain to the head or out into the arm. Try to arrive at an integrated clinical interpretation. Local pain + trigger points → neck myalgia / myofascial pain syndrome. Generalized pain + tenderness in multiple regions → consider fibromyalgia. Pain radiating to the head → consider cervicogenic headache or m. sternocleidomastoideus trigger points. Pain behind the eye/back of the head → consider occipital neuralgia.
m. trapezius
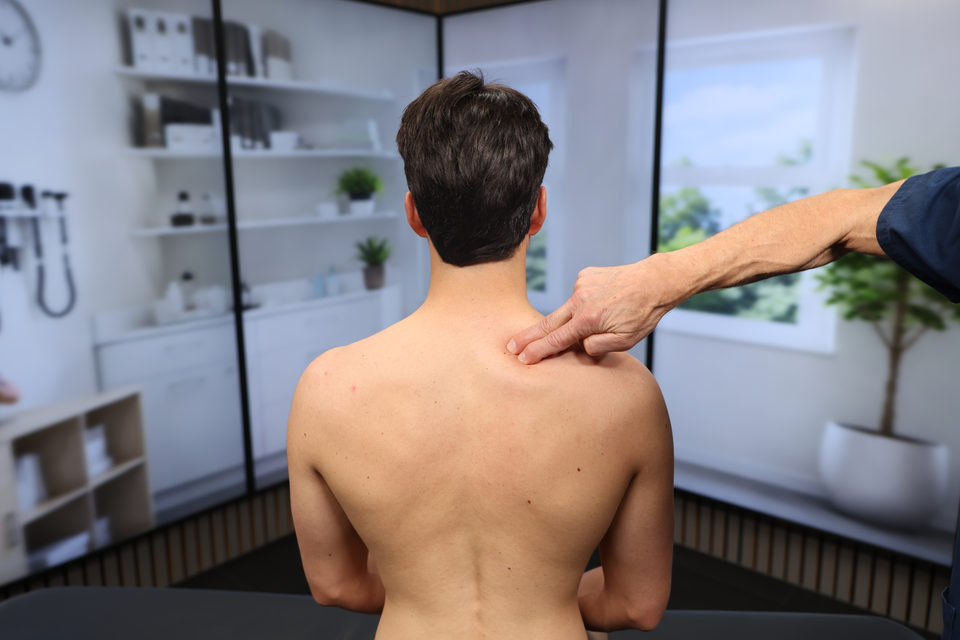
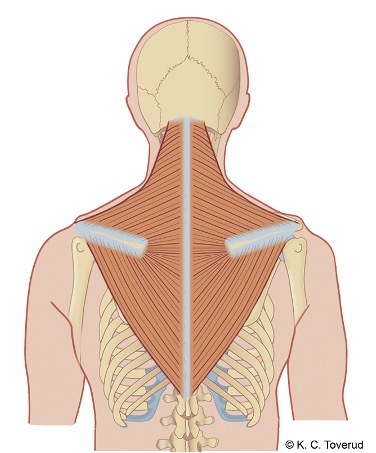
Palpate along the lateral side of the neck. The upper part of the muscle often has trigger points that can radiate up into the head and toward the forehead. Also palpate the attachment along the spine of the scapula. The middle and lower part of the muscle is palpated between the shoulder blades.
m.levator scapulae
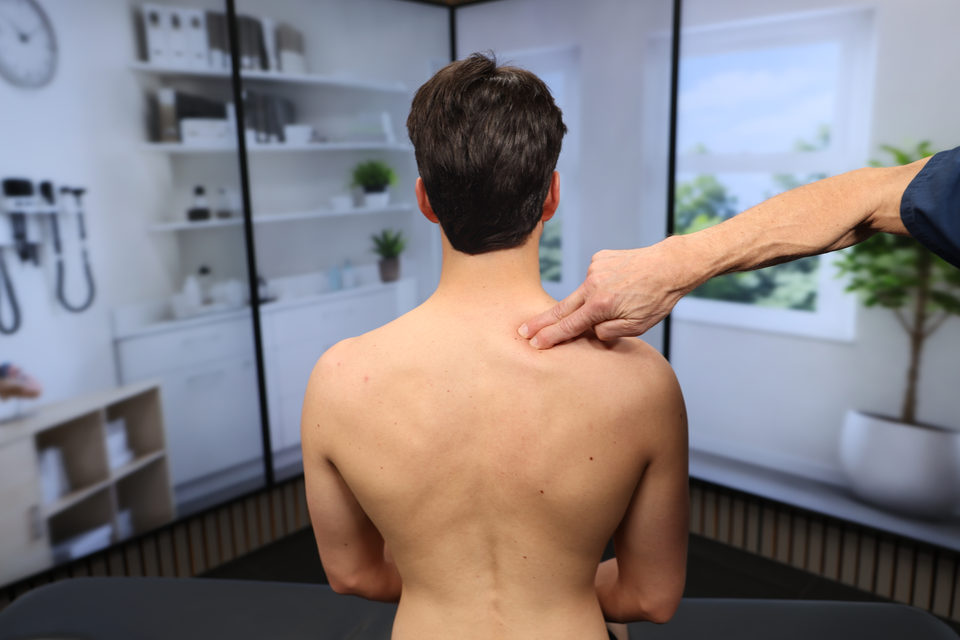
Palpate from the superior angle of the scapula and towards the cervical spine. The muscle often has trigger points that can give referred pain to the head and arm.
Mm. suboccipitalis
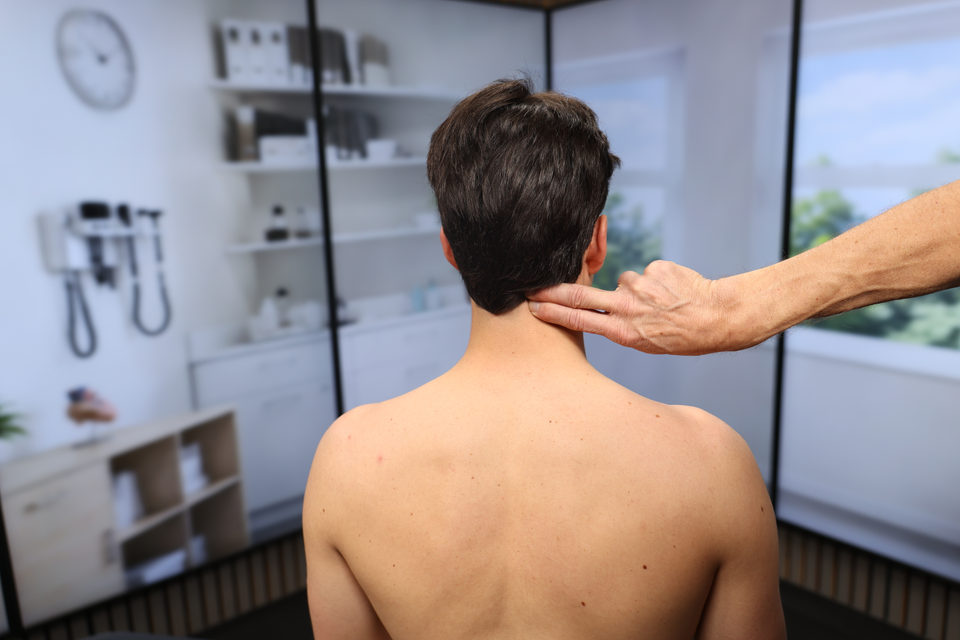
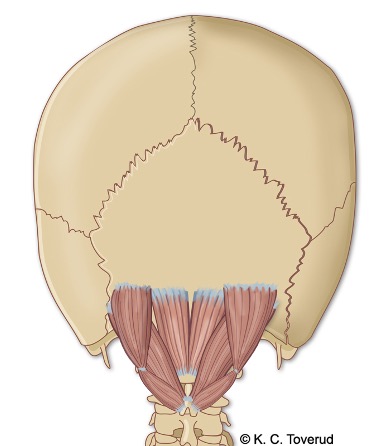
The nuchal muscles consist of four small muscles in the upper and lower cervical joints, which are covered by the m. semispinalis capitis. They are difficult to palpate accurately but can often cause tension in the upper part of the neck.
m.sternocleidomastoideus

Palpation of the muscle belly can reveal trigger points. During palpation, the patient can, in addition to local and referred pain, also experience autonomic reactions in the form of dizziness, sweating, and tinnitus.
Symptoms in fibromyalgia and neck myalgia
| Symptom/Finding | Fibromyalgia | Neck myalgia |
|---|---|---|
| Pain location | Often several regions at the same time | Localized, most often the nuchal area |
| Pain radiation | No, but migration of pains to different parts of the body | Can be pain radiation to the head |
| Trigger points | Usually not | Usually not |
| Muscle tenderness | Yes, but often in combination with abdominal pain and headache | Yes, in muscles |
Torticollis
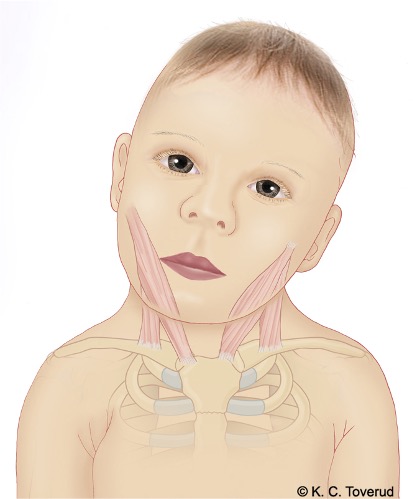
- Muscular tension and shortening of the sternocleidomastoid muscle
- Spontaneously occurring. Transient, improvement without treatment after 2-3 days
- Cervical dystonia (onset 30-45 years of age) causes prolonged muscle spasm and often twitches
Assessment of clinic based on standard examination
If you find that active and passive neck movements are positive (painful), check whether the range of motion in the neck is reduced. If the range of motion is reduced, then check whether the reduction in range of motion is symmetrically reduced or only reduced in one direction.
If the range of motion is symmetrically reduced with a hard end-feel at the end of the range of motion and with little or only moderate pain, it may indicate osteoarthritis in the neck. If you notice severe pain at the end of the range of motion, it may indicate a rheumatic disease (for example, Bechterew's disease), and if there is a history of trauma, a fracture must always be considered.
If during the examination you find asymmetrically reduced range of motion (alternatively, you may find normal range of motion but with pain at the end point of the range of motion) with pain in one direction of movement, you must consider the possibility of a disc herniation. The suspicion is strengthened if the examination also causes a tendency for radiating pain into the arm. In cases of clinical suspicion of cervical disc disease, you must proceed with a neurological examination (strength, sensation, reflexes) to clarify the degree of neurological deficits and arrive at a tentative diagnosis regarding which nerve root is affected. This forms the basis for determining how the patient should be followed up and provides a good basis for describing the condition both in the radiology referral (MRI) and in the referral to a neurosurgeon if you deem that the patient should be considered for surgery.
An asymmetric movement pattern in the neck may also indicate wear in the facet joints; the pain will then be localized in the neck without a tendency to radiate, as in the case of a herniated disc.
If, during the examination, you find normal findings in active and passive movements, but the patient reports pain when extending to the endpoint of the range of motion, this may be a warning sign, and one should then be extra attentive to whether there may be underlying serious disease, such as cervical metastasis.
If, upon examination, you find that active and isometric tests in the neck are positive, you must consider whether the isometric examination only indicates pain or whether there is both pain and reduced strength. In the latter case, with both pain and reduced strength, one must consider the possibility of a serious underlying disease, such as a cervical metastasis.
If the isometric examination shows reduced strength without pain, one must consider cervical root affection at level C2-4; this is a very rare finding.
If you only find pain during active and isometric examinations, it can indicate myalgia; you will then benefit greatly from palpation of the muscular structures in the neck to be able to locate the origin of the pain.
If during the neck examination you are unable to reproduce the patient's complaints through the clinical examination, you must consider whether there may be a "Thoracic Outlet Syndrome" (TOS), especially if the patient complains of paresthesia radiating into the arm despite a negative examination for cervical disc herniation. You must then perform relevant TOS tests to see if you can get closer to an answer regarding the patient's complaints.
Final competence
- Perform relevant clinical examination in a skilled and gentle manner
- Interpret clinical findings and be able to establish tentative diagnoses
- Suggest referral and treatment
Last updated 05.10.2026